

You probably don’t need to stop breastfeeding. De Quervain’s related wrist pain is common after birth and can usually be managed with posture changes, support and simple treatments. Start by changing how you position your arm during feeds, support your baby’s weight on a pillow instead of your wrist, and alternate sides. Paracetamol or ibuprofen can ease the pain, and a thumb spica splint helps during peak strain. See a clinician if the pain persists beyond a week or two, or if it starts limiting what you can do.
TL;DR:
- Repetitive lifting and wrist bending during baby care, especially in first pregnancies or with longer pregnancies, significantly increase the risk of developing De Quervain’s.
- Symptoms typically include pain at the thumb base that worsens with lifting, gripping, or twisting motions, particularly during diaper changes or nursing.
- Supporting the baby at breast height using high, firm nursing pillows and alternating arms during feeds can reduce mechanical strain on the wrist.
- Most treatments like splints, painkillers, and activity modifications are safe during breastfeeding and can effectively alleviate symptoms, avoiding the need for surgery in most cases.
- Persistent or worsening wrist pain beyond two weeks warrants medical evaluation for possible corticosteroid injections or further intervention.
Table of Contents
- What is De Quervain’s tenosynovitis and why do new mothers get it?
- How do you know if it’s De Quervain’s? Symptoms to watch for
- Breastfeeding positions and ergonomics that protect your wrist
- What the evidence says about breastfeeding pillows
- Pain relief and treatment options that work with breastfeeding
- When to see a doctor and what happens next
- Real adaptations mothers use and what actually helps
- A note from the author
- How the Zabbidoo nursing pillow supports a sore wrist
- FAQ
- Sources
What is De Quervain’s tenosynovitis and why do new mothers get it?
De Quervain’s tenosynovitis affects two tendons that run along the thumb side of your wrist, inside a narrow tunnel called a sheath. When those tendons get irritated, the sheath thickens and swelling restricts the tendons’ movement, so every thumb or wrist motion becomes painful.

New mothers are prone to this for a mechanical reason: feeding and caring for a baby involves constant repetitive lifting, often with the wrist bent and the thumb braced under the baby’s head or body. Add in the fluid shifts and ligament changes that come with pregnancy and the early postpartum weeks, and the tendons are working harder while the tissue around them is less resilient than usual.
Recent research backs this up. A 2024 study from Griffith University found that mechanical load, meaning repetitive lifting and holding of the baby, is a primary driver of postpartum wrist pain, and identified several factors that raise the risk:
- Having your first baby (primiparity), likely linked to less experience with efficient lifting and holding techniques.
- A pregnancy lasting longer than 40 weeks.
- A body mass index above 25.
None of these factors are things you did wrong. They describe who is more likely to develop the condition, not a failure of technique, and understanding the mechanical trigger is the first step toward reducing it.
How do you know if it’s De Quervain’s? Symptoms to watch for
The hallmark symptom is pain at the base of the thumb, right where it meets the wrist. It often builds gradually rather than appearing overnight, and tends to worsen with specific movements rather than staying constant.
Common signs include:
- Pain, swelling or tenderness directly over the thumb side of the wrist.
- Pain that spikes when you lift, grip or twist your wrist, such as picking up your baby or wringing out a wash cloth.
- A pulling or aching sensation that can run partway up the forearm.
- Difficulty with tasks that combine gripping and wrist movement at once.
Certain everyday actions tend to trigger or worsen the pain: lifting your baby out of a cot or bassinet, changing a nappy, pushing a pram, or holding a bottle for an extended feed. Notice which specific movements set it off. If you can describe the pattern clearly, it saves time with your GP or hand therapist and helps rule out other causes of wrist pain.
When you see a clinician, it helps to be specific rather than general. Instead of “my wrist hurts”, try describing which movements trigger it, how long the pain lasts afterwards, whether it is improving or worsening week by week, and which daily tasks it now interferes with, such as buttoning clothes, opening jars or lifting your baby one-handed. That level of detail helps a GP or hand therapist distinguish De Quervain’s from other causes of wrist pain and plan treatment faster.
Breastfeeding positions and ergonomics that protect your wrist
The biggest single change you can make is bringing your baby up to breast height, rather than leaning your body down to your baby. Leaning forward forces your supporting arm and wrist into the exact bent, loaded position that aggravates the tendons. A firm, higher pillow under your baby closes that gap without extra effort on your part.
Three holds are worth adapting specifically for a sore wrist:
- Cradle hold: rest your baby fully on a supportive pillow at breast height, with your forearm along the top of the pillow rather than under your baby’s weight, so your wrist stays straight.
- Cross-cradle hold: use the opposite arm to support your baby’s head while your feeding-side arm rests flat along the pillow, keeping the wrist neutral instead of curled under the head.
- Side-lying feed: lie on your side with your baby facing you, removing arm-support demands altogether, useful for night feeds when your wrist is most fatigued.
Beyond the hold itself, where you place your arm matters as much as how you hold your baby. A firm pillow, a tightly folded towel, or a stable high-lift nursing pillow placed under your forearm (not just under your baby) stops your wrist from bearing weight it was never designed to carry during long feeds. Our guide to infant feeding positions walks through the setup for each hold in more detail.
A few practical habits make a real difference over the course of a day:
- Alternate which arm supports your baby during feeds, rather than always favouring one side.
- Pace physically demanding tasks across the day instead of batching them, and ask a partner or family member to help with lifting, laundry or anything involving repeated gripping.
- Change your nappy-change technique: rest your baby on a change table at waist height rather than on a low surface that forces you to bend and twist, and support their weight with your forearm rather than gripping tightly with your thumb.
- Choose a feeding chair with solid armrests, add a footstool if your feet don’t rest flat, and keep your pram and feeding supplies within easy reach so you’re not twisting or overreaching during the day.
Pro Tip: Set up your feeding station before you sit down, pillow, water, phone, everything in reach, so you’re not twisting sideways mid-feed to grab something.
A newborn’s feeding routine changes fast in the early weeks, so it’s worth revisiting your setup as your baby grows. Our 2026 feeding posture guide covers the adjustments worth making as your baby’s weight and alertness change.
What the evidence says about breastfeeding pillows
A randomised controlled trial tested whether a breastfeeding pillow actually reduces physical discomfort during feeds, rather than just feeling more comfortable in theory.
A randomised controlled trial found that mothers using a breastfeeding pillow reported significantly lower discomfort scores across repeated assessments than those feeding without one. That matters for wrist pain specifically, because discomfort during feeding is closely tied to how much weight your arm and wrist are bearing unsupported.
Not every pillow delivers that benefit equally. When choosing one, a few features matter more than price or branding:
- Height and lift: a pillow that brings your baby close to breast height, so you’re not leaning down or hiking your shoulder up to compensate.
- Stability under weight: a pillow that holds its shape through a full feed rather than compressing flat within minutes, which forces your arm to take over the support it was supposed to provide.
- Compression resistance: fill that springs back between feeds rather than flattening permanently after weeks of daily use.
- A washable, removable cover: feeds are messy, and a cover you can throw in the wash matters more than it sounds.
How you use the pillow matters as much as which one you buy. Position it so your forearm, not just your baby, rests on the firm surface, and check that your wrist stays straight rather than curling over the pillow’s edge to reach your baby. A pillow that sits too low still invites you to lean forward, which defeats the purpose. Australian breastfeeding guidance consistently points to firm elbow support and good chair setup as the baseline for comfortable, sustainable feeding positions, and the right pillow height is what makes that support possible.
Pain relief and treatment options that work with breastfeeding
Most first-line treatments for De Quervain’s are compatible with breastfeeding, which is often the first worry mothers raise.
- Paracetamol and ibuprofen are generally considered safe first-line pain relief options while breastfeeding, according to Healthdirect’s medicines and breastfeeding guidance. Always check the dose against the packet and your own health history, and ask a pharmacist if you’re taking anything else.
- Thumb spica splinting immobilises the thumb and wrist to let the irritated tendons rest. You don’t need to wear it around the clock: many mothers wear it overnight and during high-strain tasks like lifting or long feeds, and remove it for tasks needing fine motor control, such as fastening clothing or handling small objects.
- Ice and activity modification reduce inflammation and give the tendons a break, and a physiotherapist or hand therapist can set you up with gentle stretching and strengthening exercises once the acute pain eases.
- Corticosteroid injections, delivered by a specialist, are often effective and are usually compatible with breastfeeding, though it’s worth discussing timing and any rare effects on milk supply with your clinician beforehand, per the same Healthdirect guidance.
- Surgery is reserved for cases where conservative treatment and injections haven’t worked, and is considered a last resort rather than a first step.
A common misconception is that any medical treatment means pausing breastfeeding. In practice, clinicians routinely reassure mothers that most conservative and specialist options, from analgesics to splints to injections, can be used safely without interrupting feeding, a point echoed in clinical commentary from The Well by Northwell. If you need a ready-made splint rather than a fitted one from a therapist, a medium thumb spica wrist brace is one option available for left or right wrists. For more on fitting a splint around feeding routines, see our guide to wrist support during feeding.
When to see a doctor and what happens next
Most postpartum wrist pain eases with rest, support and the self-care steps above. It’s time to book an appointment when:
- Pain persists or worsens beyond seven to fourteen days despite rest and splinting.
- You notice a progressive loss of grip strength or thumb movement.
- The pain is severe enough to interfere with feeding, lifting your baby, or basic daily care.
Start with your GP, who can assess the wrist, rule out other causes and refer you on if needed. An allied health professional, typically a physiotherapist, hand therapist or occupational therapist, can fit a proper splint, build an exercise plan and give you pragmatic, caregiving-aware advice rather than blanket rest instructions that don’t fit life with a newborn.
In clinic, expect a physical assessment, a conservative management plan covering splinting and activity changes, and, if symptoms don’t settle, consideration of an ultrasound-guided corticosteroid injection. According to Healthdirect, steroid injection resolves symptoms in up to 8 in 10 people, and surgery is only considered when injections fail to bring relief, as outlined on Healthdirect’s surgery page.
Real adaptations mothers use and what actually helps
Qualitative research into first-time mothers’ experiences with De Quervain’s tenosynovitis found the condition disrupts basic caregiving tasks, with mothers describing moments as specific as struggling to change a nappy, according to a qualitative study of new mothers’ experiences. The same research documented how mothers adapt in practice rather than simply resting, which isn’t realistic with a newborn:
- Using a scooping lift technique, sliding both forearms under the baby rather than pinching with the thumb and fingers.
- Feeding side-lying to remove arm-support demands during night feeds.
- Switching which hand does the gripping and lifting through the day, and asking a partner or family member to take over high-strain tasks.
Hand therapists working with this group tend to favour flexible splint schedules over rigid all-day wear, reserving the splint for night-time and for specific high-load tasks rather than insisting on constant use, since the research notes that task-specific adaptation and family support are far more workable for new mothers than blanket rest advice.
These findings line up closely with what an ergonomic nursing pillow is designed to solve. A higher 18cm lift brings your baby to breast height instead of asking your wrist to bridge the gap, compression-resistant fill keeps that support stable through a full feed rather than collapsing, and a stability-focused design cuts down on the constant repositioning that aggravates already irritated tendons.
A note from the author
Caring for a newborn while every lift and nappy change sends pain through your wrist is exhausting in a way that’s hard to explain to anyone who hasn’t lived it. You’re not imagining the pain, and you’re not failing by needing support to manage it.
The reassuring part is that most of what helps, posture changes, a good pillow, paracetamol, a splint worn only when you need it, is simple and safe to use while breastfeeding. You don’t have to choose between feeding your baby and treating your wrist.
— Marietjie
How the Zabbidoo nursing pillow supports a sore wrist
The mechanics in this article point to one practical fix: stop your wrist from bridging the gap between your arm and your baby. That’s exactly what a higher, more stable pillow is for.
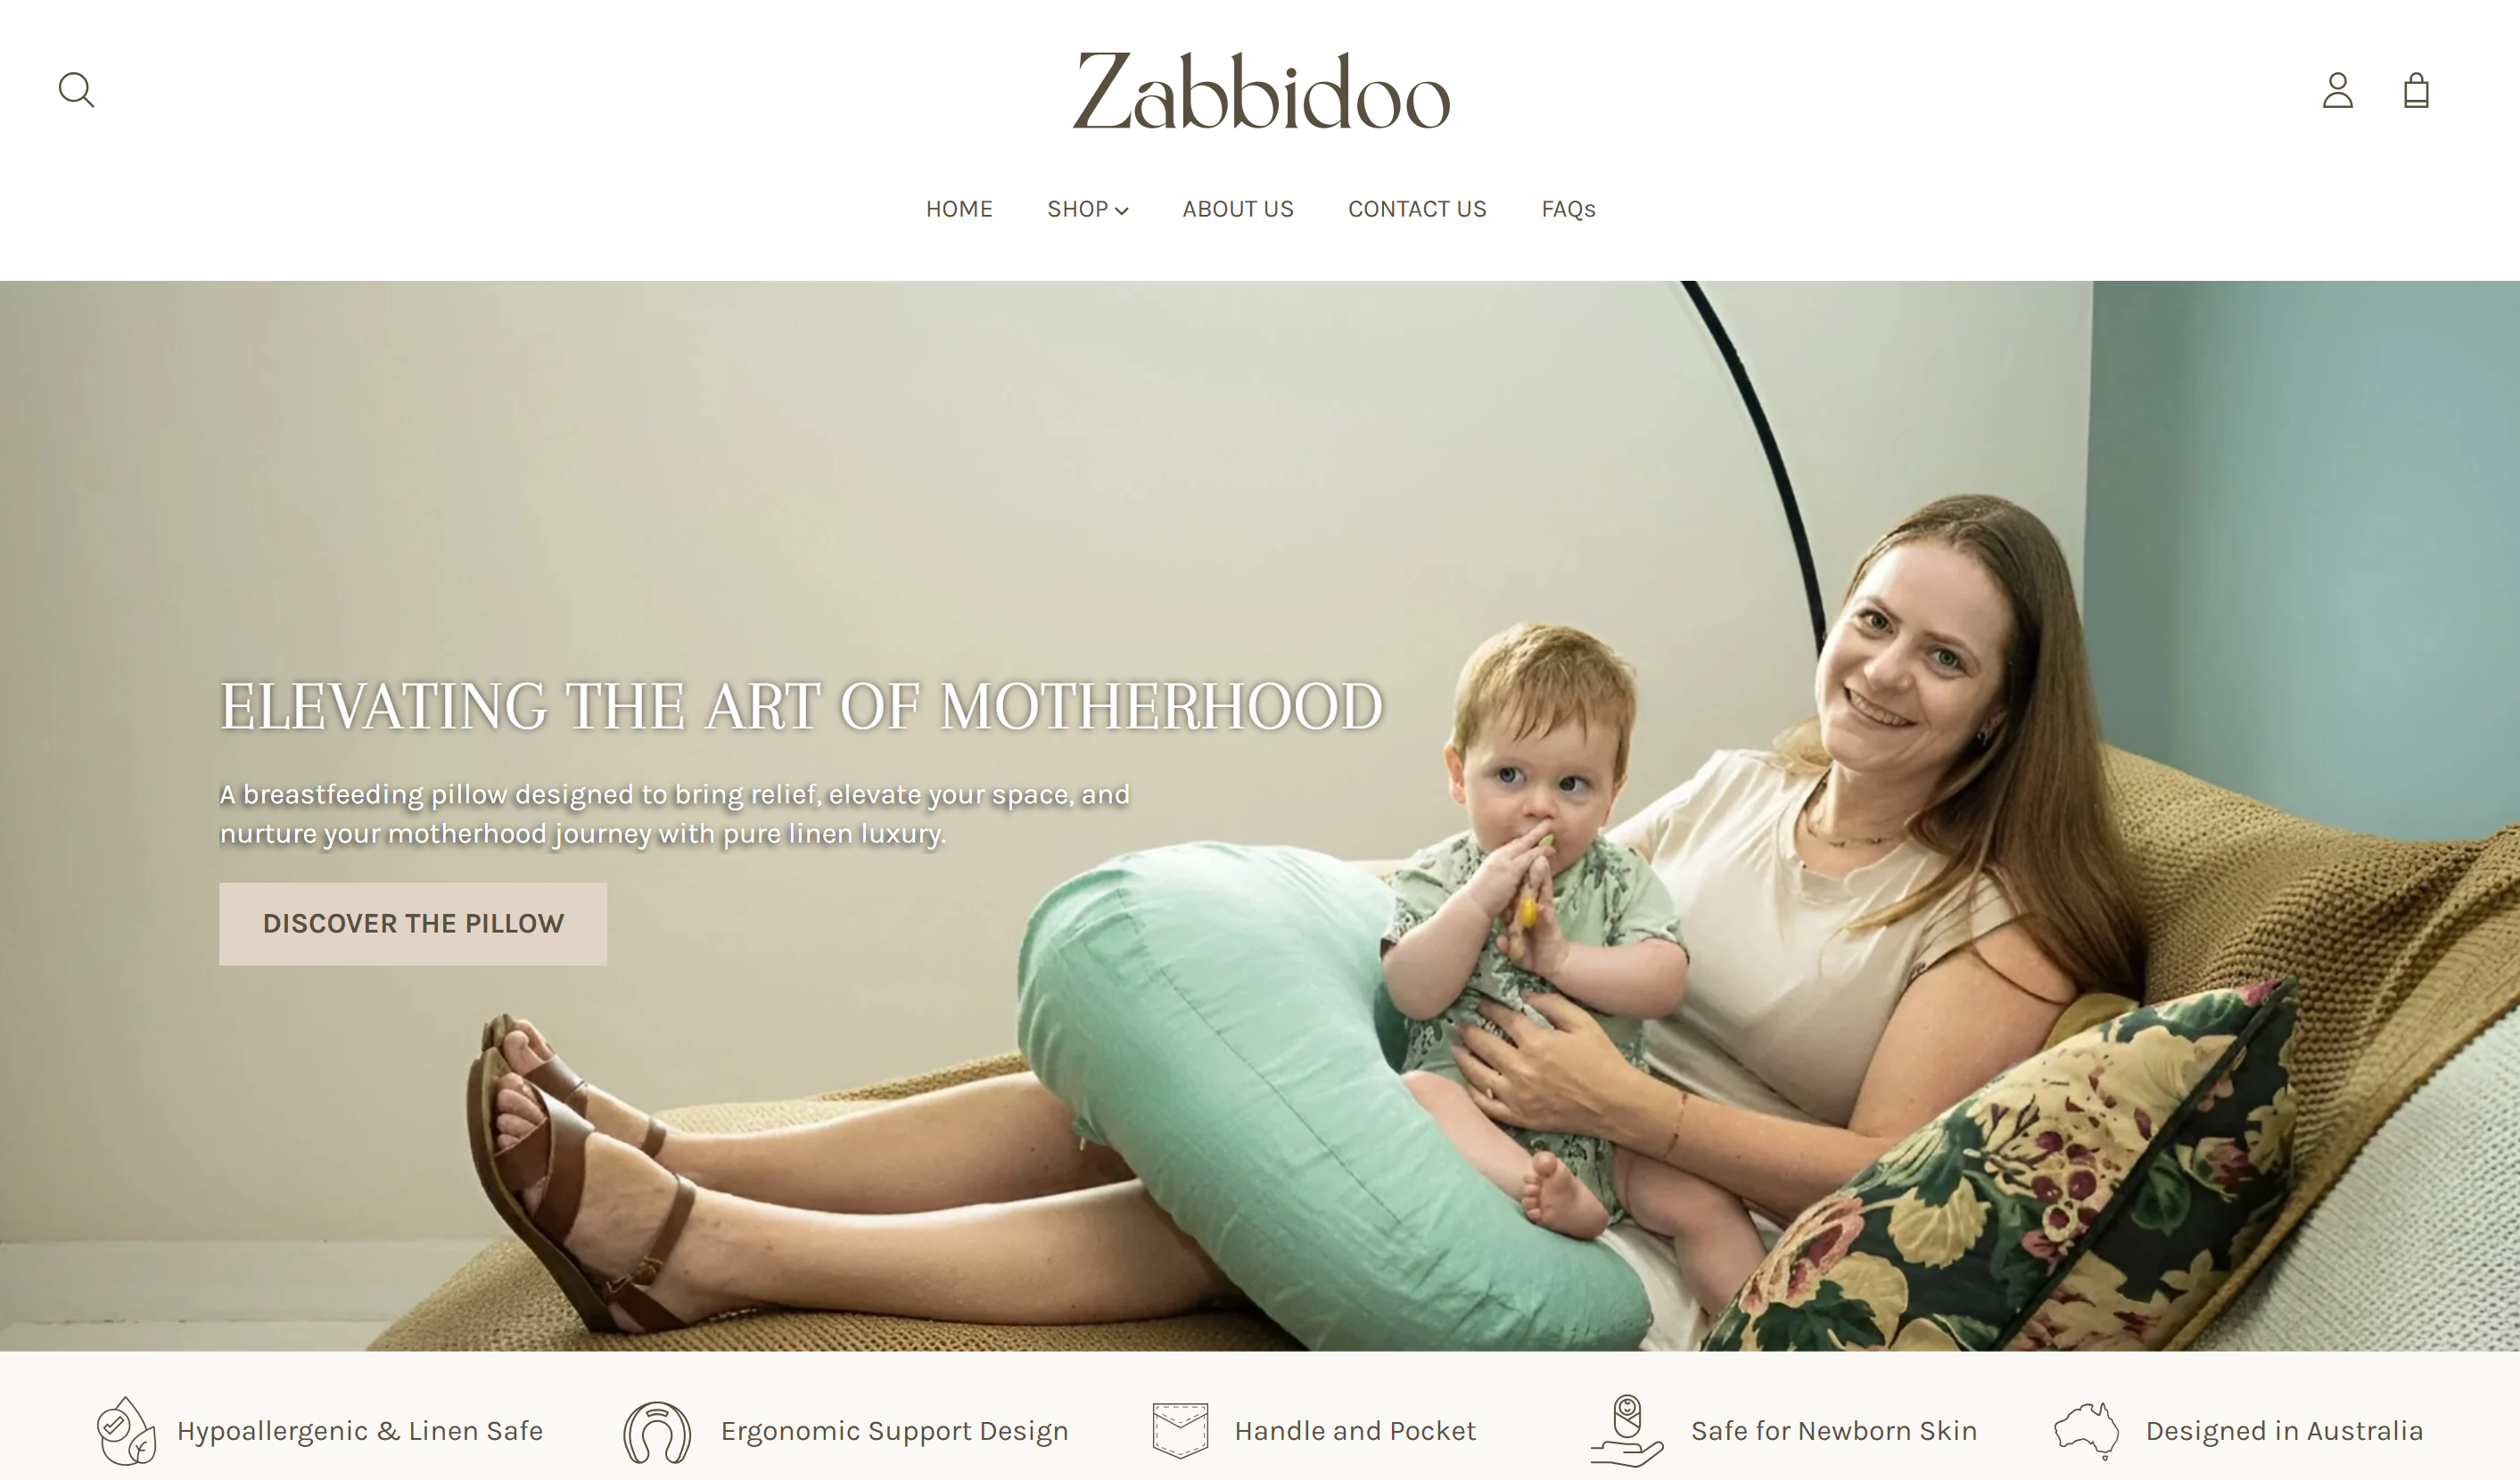
A nursing pillow with a higher lift brings your baby up to breast height instead of you leaning down or your wrist bearing the shortfall. A compression-resistant fill helps keep that height through a full feed rather than flattening quickly, which matters for the long, slow feeds of the early weeks when wrist fatigue sets in. A stability-focused shape can also mean less constant repositioning, one of the triggers that aggravates an irritated tendon sheath.
Before buying any nursing pillow, check three things: does it hold its height under your baby’s actual weight, does the cover come off for washing, and is it firm enough that your forearm doesn’t sink into it. The pillow cover can be made from breathable linen and comes off for machine washing, and the pillow doubles for tummy time and general support once feeding settles down.
You can view the full feature set and buy the Nursing Pillow directly, or see pricing and details on the Zabbidoo nursing pillow page.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Can breastfeeding cause De Quervain’s tenosynovitis?
Breastfeeding itself doesn’t cause De Quervain’s, but the repetitive lifting, holding and bent-wrist postures involved in caring for a newborn are a recognised mechanical trigger, according to Griffith University research. Hormonal and fluid changes around pregnancy can also make tendons more vulnerable to irritation in the same period.
Will “mommy thumb” go away?
For most mothers, symptoms ease with rest, splinting and posture changes as the repetitive strain reduces and tissues recover. If pain persists beyond a week or two or keeps worsening, see a GP, since further treatment such as a corticosteroid injection resolves symptoms in up to 8 in 10 people according to Healthdirect.
What happens if you ignore De Quervain’s tenosynovitis?
Left untreated, the pain and swelling tend to persist or worsen, and grip strength and thumb movement can decline further, making everyday caregiving tasks harder. Early self-care and a timely GP visit generally lead to a faster, easier recovery than waiting for it to resolve on its own.
Will De Quervain’s tenosynovitis go away after pregnancy?
For many mothers, symptoms improve as hormonal and fluid shifts settle and as lifting technique and support improve over the following weeks and months. It doesn’t resolve for everyone without treatment, so ongoing or worsening pain is worth assessing rather than waiting out indefinitely.
Sources
- The use of breastfeeding pillow to reduce discomfort for breastfeeding mothers (RCT)
- Healthdirect — medicines and breastfeeding guidance
- Griffith University research on risk factors for postpartum De Quervain’s