

Yes, you can breastfeed after a C-section, and most mothers do so successfully with the right early support. Ask for skin-to-skin contact as soon as you and your baby are assessed as well, request lactation help while you’re still in recovery, and try a side-lying or football hold that keeps weight off your incision. Most anaesthetics and standard pain medicines used after surgery are compatible with breastfeeding, but always confirm the specifics with your clinical team.
TL;DR:
- Breastfeeding after a C-section generally works well with early skin-to-skin contact, prompt lactation help, and positions that avoid pressure on the incision.
- The football hold, side-lying, and reclined positions are recommended to keep weight off the wound while ensuring effective latching and comfort.
- Delayed milk onset beyond 72 hours is common in C-section recoveries, so frequent feeding, hydration, and skin-to-skin are crucial to support supply.
- Using a high, firm nursing pillow can improve positioning and reduce strain during feeds, especially when bending or lifting is uncomfortable.
Table of Contents
- Best positions and setup that protect your incision
- When to start breastfeeding and settling into an early rhythm
- Supporting your supply and spotting delayed milk coming in
- Expressing, pumps and when to use them after surgery
- Managing pain and protecting your incision while feeding
- Who can help, warning signs and follow-up checks
- How the right nursing pillow supports recovery and latch
- Give yourself the same patience you’d give a friend
- A practical comfort aid for feeding after surgery
- Authoritative resources to read next
- Sources
- FAQ
Best positions and setup that protect your incision
The right position after a caesarean isn’t about comfort alone. It’s about keeping any pressure off your wound while still getting a deep, effective latch.
The football (clutch) hold tucks your baby under your arm, facing you, with their legs pointing towards your back rather than across your lap. This keeps your baby’s weight entirely off your abdomen. Pack pillows firmly under your arm and along your side so your baby sits at breast height instead of you leaning down to reach them.
Side-lying works well once you can roll onto your side comfortably. Lie with a pillow supporting your back and one between your knees, and bring your baby in facing you at chest level, tummy to tummy. This position also lets you rest while feeding, which matters in the first exhausting days.

The reclined or laid-back hold has you leaning back at a comfortable angle with your baby lying on your chest, away from your incision line. Gravity does some of the work of holding your baby in place, which helps when your abdominal muscles are still sore.
In every position, the goal is the same: bring your baby up to you rather than folding yourself forward. The Australian Breastfeeding Association recommends pillows or supports specifically to reduce pressure on the wound while breastfeeding.
- Ask a nurse or your partner to position pillows before they hand your baby to you, especially if you have an IV line, catheter or drain restricting movement.
- If one arm is restricted, use the football hold on your unaffected side first.
- If latching feels shallow or painful, break the seal gently with a clean finger and try again rather than pushing through pain.
Pro Tip: Ask hospital staff to raise your bed or add an extra pillow behind your back before feeds. Small height adjustments make a bigger difference than most people expect.
When to start breastfeeding and settling into an early rhythm
Skin-to-skin contact and a first breastfeed should begin as soon as you and your baby are both assessed as well, which for many caesarean births is within the first hour or two, and the Royal Hospital for Women’s clinical guidance recommends skin-to-skin and breastfeeding or hand expression within the first 24 hours. If you’re separated from your baby for medical reasons, start hand expressing as early as you can rather than waiting.
Skin-to-skin contact isn’t just comforting. It helps trigger your baby’s natural feeding instincts and supports the release of oxytocin, the hormone that drives your milk-ejection reflex.
Once feeding begins, aim for roughly eight to twelve breastfeeds or expressing sessions across 24 hours, guided by your baby’s hunger cues rather than the clock. Early cues include rooting, hand-to-mouth movements and lip-smacking, well before crying starts.
- Feed on cue rather than a strict schedule during the first weeks.
- Wake a sleepy newborn for a feed if several hours have passed during the day.
- Watch for six or more wet nappies daily by day five as a rough sign of adequate intake.
A caesarean birth is a recognised risk factor for delayed onset of lactogenesis II, the stage when milk volume increases, according to clinical guidance from the Royal Hospital for Women. Knowing this in advance means you’re less likely to panic if your milk takes a little longer to increase in volume.
Supporting your supply and spotting delayed milk coming in
Delayed onset of lactogenesis II is defined as milk production starting beyond 72 hours after birth, and caesarean section is one of the documented risk factors, according to the Royal Hospital for Women’s clinical brief on the condition. Knowing what to watch for, and what to do about it, protects your supply during those crucial early days.
- Feed or express frequently, aiming for eight or more sessions in 24 hours.
- Hand express for a few minutes after or between feeds if your baby isn’t clearing the breast well.
- Stay well hydrated and keep nutritious snacks within reach, since recovery and milk production both draw on your energy.
- Maximise skin-to-skin time whenever you can, even outside of feeds.
Ask your midwife or lactation consultant for a baby weight check and a suck assessment if feeding seems ineffective or your baby seems unsettled after most feeds. Hospitals often use a structured feed chart to track suck quality and guide decisions on next steps, including referral to lactation services. If supplementation becomes medically necessary, cup or syringe feeding is generally preferred over a bottle in the early days, but follow the specific advice your clinical team gives you.
Expressing, pumps and when to use them after surgery
If your baby can’t feed directly in the first hour or two, hand expression is the recommended way to collect the small amounts of early colostrum, using clean hands and a small cup or syringe to catch what comes.
- Massage the breast gently towards the nipple, then compress and release rhythmically rather than pulling.
- Collect drops into a sterile container and label it with the time and date for hospital staff.
- Repeat every two to three hours if your baby remains separated from you.
Hospital-grade pumps are typically introduced around 24 to 36 hours if your baby still can’t breastfeed directly, according to clinical guidance on first breast expression. Double pumping, expressing both sides at once, tends to stimulate supply more effectively than single sessions spaced further apart.
Try to mirror a newborn’s feeding rhythm, including through the night, since prolactin, the hormone driving milk production, peaks overnight. Skipping overnight sessions in the early weeks can slow your supply from building well.
Pro Tip: Keep a simple log of times and volumes on your phone. It sounds unnecessary until day three, when exhaustion makes it hard to remember your last session.

Managing pain and protecting your incision while feeding
Good pain control isn’t a luxury after a caesarean, it directly affects your ability to feed. Pain can inhibit the let-down reflex, so staying ahead of discomfort actually supports your milk flow rather than just your comfort.
Most pain relief medicines commonly used after a C-section are compatible with breastfeeding, according to guidance from the Mayo Clinic, though you should always confirm specifics with your own clinical team.
- Place a firm pillow across your lap or under your baby before lifting them, rather than twisting or leaning to pick them up.
- Wear loose, soft clothing that doesn’t press on your wound during feeds.
- Ask a partner or nurse to hand your baby to you rather than reaching or bending yourself.
- If you’ve had a general anaesthetic or heavy sedation, wait until you’re fully alert before breastfeeding directly, using hand expression and skin-to-skin in the meantime.
Keep a note of exactly which medicines you’ve been given and when, particularly if community midwives or child health nurses take over your care after discharge.
Who can help, warning signs and follow-up checks
You don’t have to work this out alone. In hospital, ask specifically for a lactation consultant visit and a written breastfeeding plan before you’re discharged, not just general midwife support.
After you’re home, the Australian Breastfeeding Association offers a helpline and local groups, and a private IBCLC can visit for more hands-on, one-to-one support if problems persist.
- Seek urgent review if your baby has lost significant weight, has fewer than six wet nappies daily by day five, or seems persistently lethargic or hard to wake for feeds.
- Contact your GP or hospital promptly if your incision becomes red, hot, swollen or starts leaking, or if you develop a fever, all possible signs of wound infection.
- Get checked for mastitis if you notice a hot, painful, red patch on your breast alongside flu-like symptoms.
Arrange for your baby to be weighed by day three, and ask your midwife how to book a follow-up visit or referral if feeding still feels difficult.
How the right nursing pillow supports recovery and latch
The core problem with most standard nursing pillows is height: they sit low, so you end up leaning down and forward to reach your baby, which puts direct strain on a fresh incision. A nursing pillow with a higher lift can help bring your baby up to breast height, so you can stay upright.
Compression resistance matters here too. A pillow that flattens under a newborn’s weight forces you back into that forward lean within minutes, which defeats the purpose. Look for firm, stable support, a breathable, washable cover, and a shape that holds up through a full feeding session rather than needing constant repositioning.
- Position the pillow so its front edge sits just above your incision line, acting as a soft barrier rather than direct pressure.
- Ask a partner to help settle the pillow into place during those first standing-up-and-sitting-down days when bending is uncomfortable.
Pro Tip: Set the pillow up before you feel the urge to feed. Fumbling with positioning while a hungry newborn cries adds stress you don’t need in the first week.
Give yourself the same patience you’d give a friend
Recovering from surgery while learning to breastfeed is genuinely hard, and most of what feels like failure in the first week is just the normal, slow start that most mothers go through. A feed that takes forty minutes today will take ten in a month.
Let people bring you meals, hold the baby while you sleep, and handle the washing. Your job right now is healing and feeding, nothing else, and asking for help with either one is not a setback.
— Marietjie
A practical comfort aid for feeding after surgery
If you’re looking for one thing to make early feeds easier on your body, A nursing pillow designed with a higher lift, compression-resistant fill, and a breathable cover can keep your baby supported at breast height without you leaning forward.
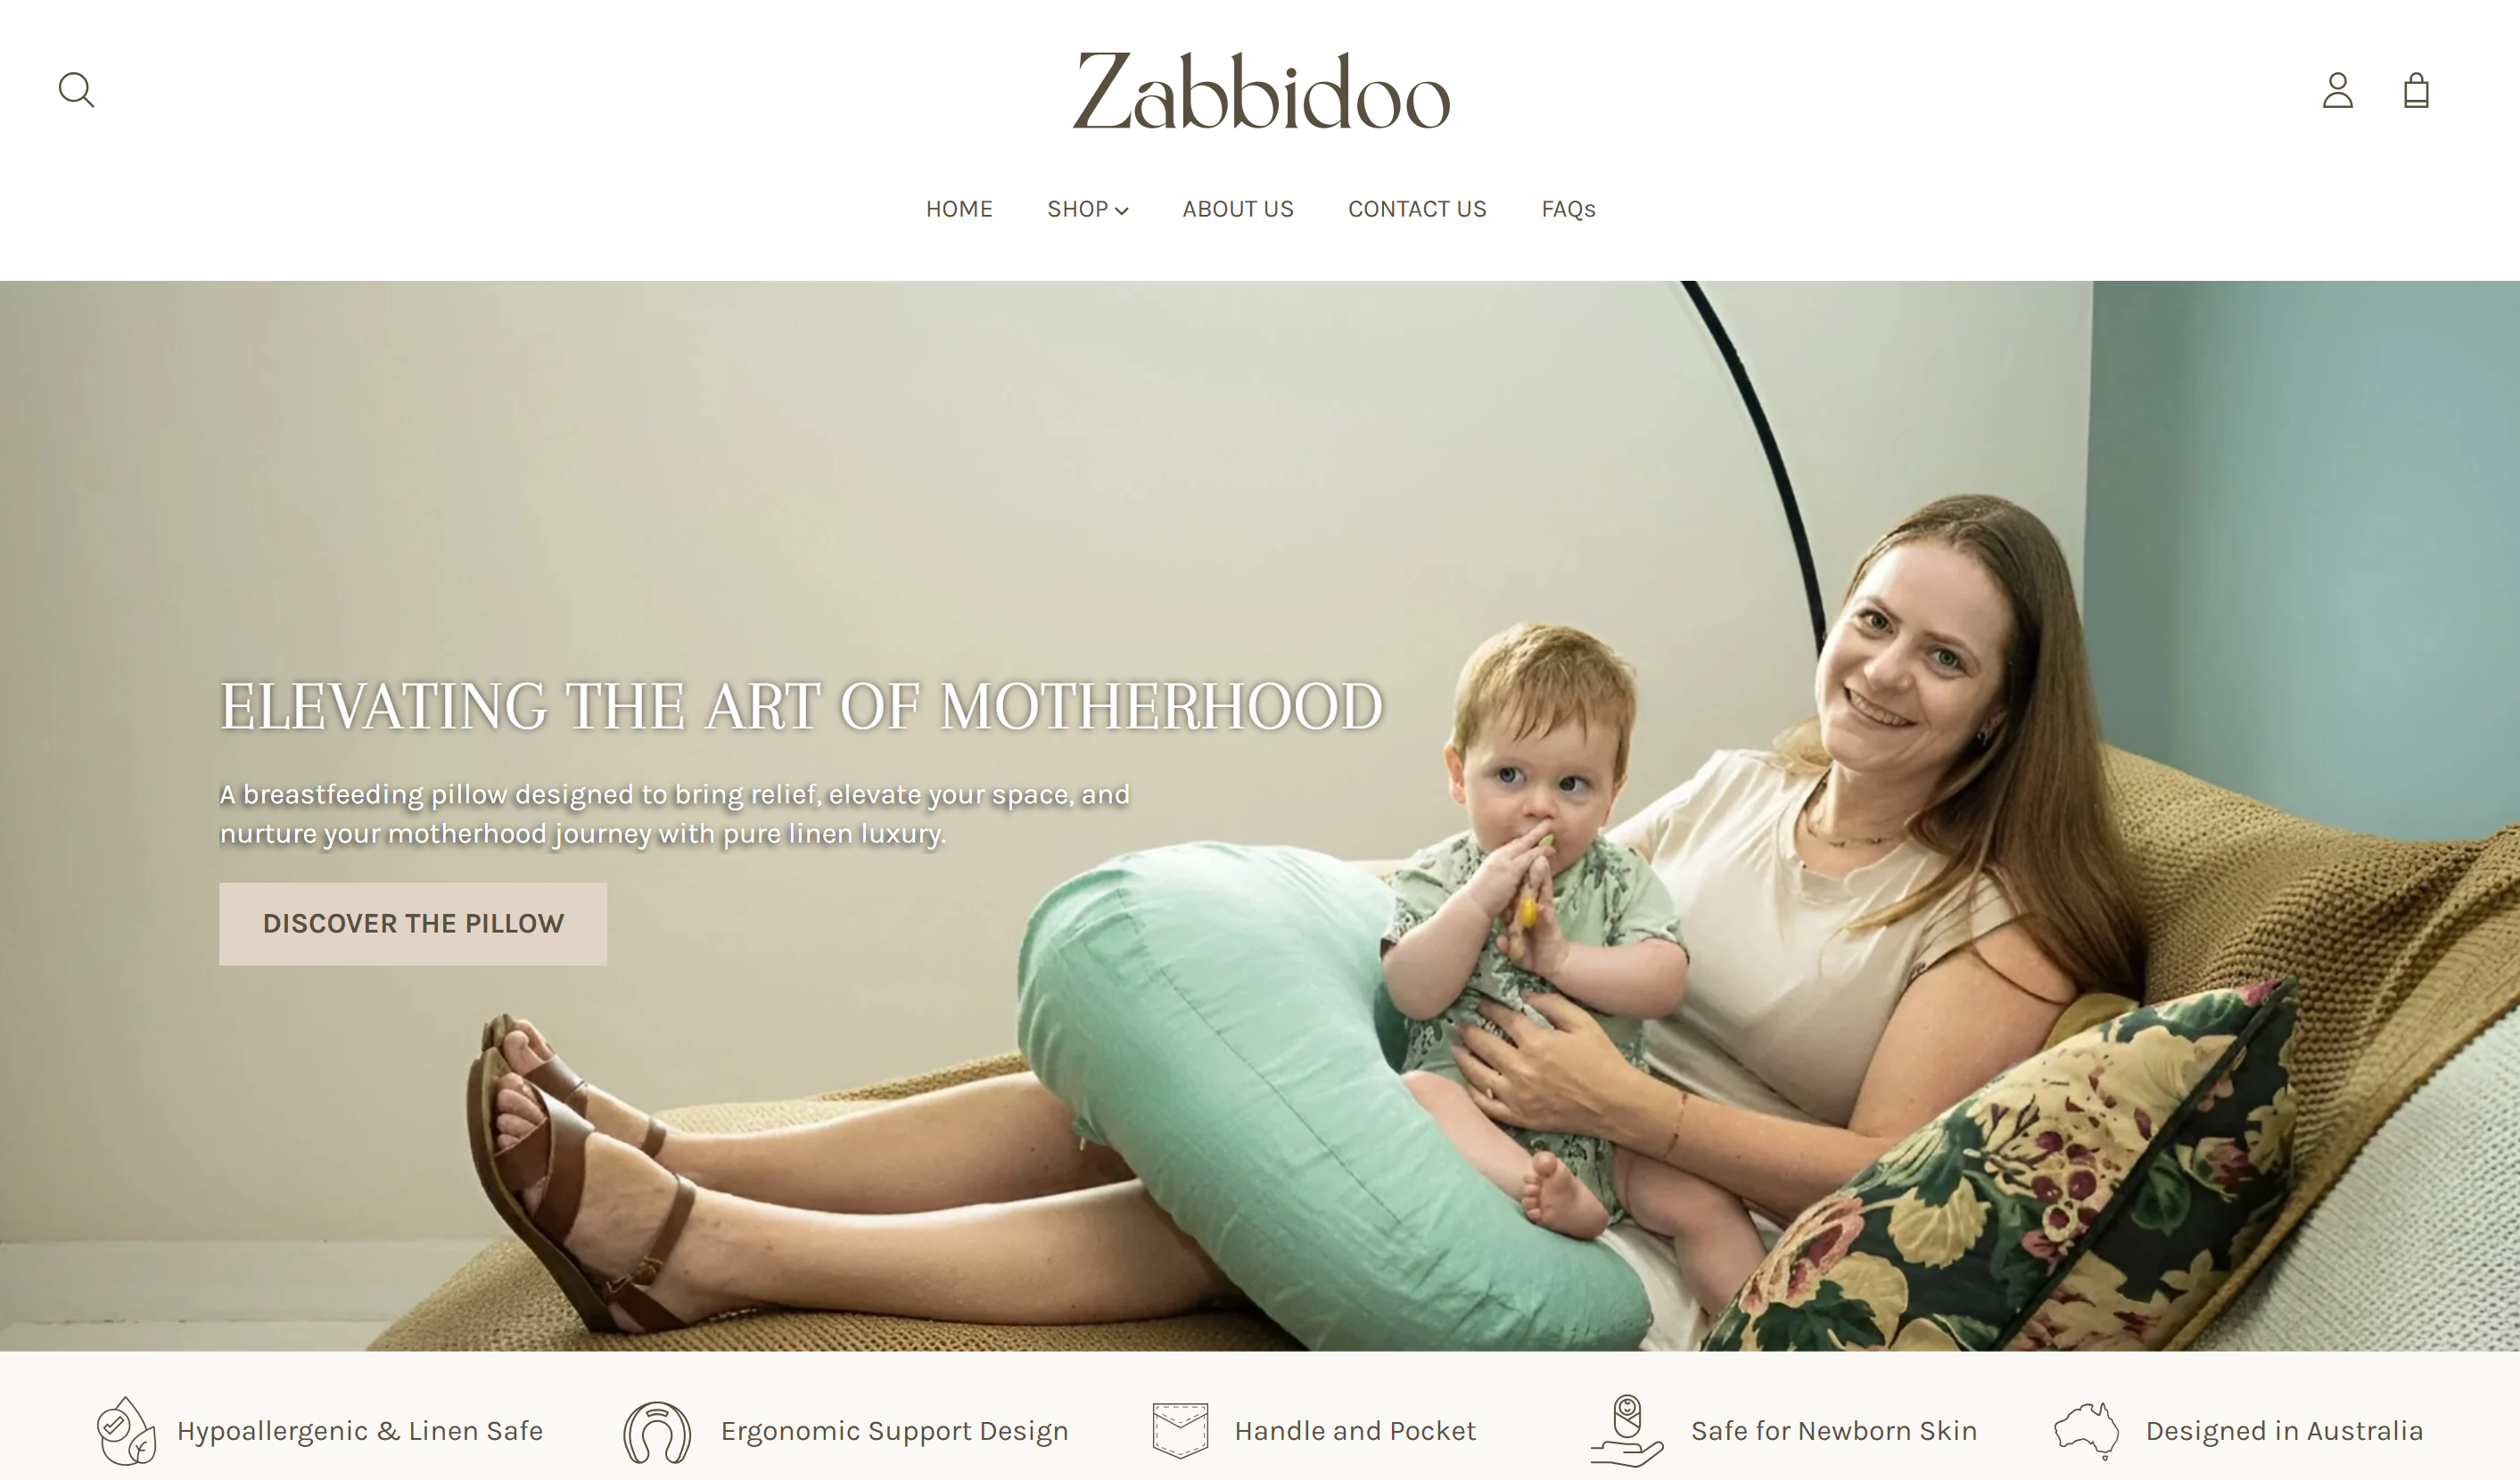
- In the football hold, it tucks under your arm and keeps your baby’s weight fully off your abdomen.
- In side-lying, it slots behind your back for support while you rest through a feed.
You can view the full nursing pillow details, including returns and support information, on the product page.
Authoritative resources to read next
For clinical detail beyond this guide, the Royal Hospital for Women’s breastfeeding after caesarean guidance and the NHMRC’s infant feeding guidelines cover hospital practice and national recommendations in full. The Australian Breastfeeding Association and Mayo Clinic offer further practical, how-to detail on positioning and recovery.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Breastfeeding after a caesarean birth | Royal Hospital for Women (SESLHD)
- NHMRC infant feeding guidelines
- Breastfeeding after a caesarean birth | Australian Breastfeeding Association
- C-section recovery and breastfeeding (Mayo Clinic)
FAQ
Why is breastfeeding harder after a C-section?
Surgery, pain and sometimes separation from your baby can delay the first feed and make positioning harder while your incision heals. Caesarean birth is also a recognised risk factor for delayed onset of lactogenesis II, meaning your milk volume may increase a little later than average.
How long after a C-section can you start breastfeeding?
You can generally start as soon as you and your baby are both assessed as medically well, which is often within the first hour or two. Clinical guidance recommends skin-to-skin contact and breastfeeding or hand expression within the first 24 hours after birth.
How to help breast milk come in after a C-section?
Frequent stimulation is the key lever: feed or express at least eight times in 24 hours, use hand expression between feeds if needed, and maximise skin-to-skin contact. Staying hydrated and eating well also support your body through this stage, and a lactation consultant can check your baby’s latch and weight if milk seems slow to increase.
How long does it take for milk to dry up if you never breastfeed?
This varies from person to person and isn’t precisely documented for every case, so it’s best discussed with your midwife or GP if it’s relevant to your situation. What’s better established is the reverse: frequent early stimulation, whether by breastfeeding, hand expression or pumping, is what builds and maintains supply.