

Baby sliding during feeds is usually a latch, flow, or positioning problem, not something you’re doing wrong. Bring your baby right up to the breast, chin leading in, and check that ear, shoulder and hip sit in one line before you latch. If pain, poor weight gain, or choking continues, see a lactation consultant.
TL;DR:
- Most sliding during feeds results from shallow latch, overactive let-down, or discomfort, not from caregiver mistakes.
- Proper positioning involves bringing the baby up to the breast with aligned ear, shoulder, and hip, using holds like cross-cradle or laid-back.
- Managing fast flow involves backward leaning and compressions; slow flow requires frequent breaks, compressions, and skin contact.
- Persistent sliding after trying positioning adjustments may indicate tongue-tie, reflux, congestion, or neck tension requiring professional assessment.
- A nursing pillow with adequate lift and stability, like the Zabbidoo Nursing Pillow, can significantly reduce sliding and improve latch stability during feeds.
Table of Contents
- What causes baby sliding during feeds and what are the warning signs?
- How do you position baby to stop them sliding?
- How do you manage fast or slow milk flow during feeds?
- When does sliding point to something more than positioning?
- What safety rules matter while you’re troubleshooting?
- Why does posture support actually reduce sliding?
- A quick word on treating feeding as a two-way skill
- Where a properly designed nursing pillow fits in
- Where to read more
- Sources
- FAQ
What causes baby sliding during feeds and what are the warning signs?
Most sliding comes down to one of three things: a latch that’s too shallow, milk moving faster than baby can manage, or a body position that’s fighting gravity from the start.
A shallow latch is the most common culprit. Baby takes just the nipple rather than a full mouthful of breast tissue, which means there’s nothing to anchor them in place. They slip, resettle, slip again. You’ll usually hear a clicking sound as suction breaks, notice the areola still visible above baby’s top lip, and feel nipple pain that doesn’t ease after the first thirty seconds. A baby-led attachment approach, where baby does more of the work finding the breast themselves, tends to produce a deeper latch than a parent steering baby’s head onto the nipple.
Overactive let-down (sometimes called OMER, or oversupply) does the opposite. Milk arrives too fast and too forcefully, so baby pulls back to cope, coughs, sputters, or comes off entirely to catch their breath. If this sounds familiar, you’re not alone. It’s common enough that lactation resources treat it as a distinct feeding pattern with its own fixes.
Then there’s discomfort. A baby dealing with trapped wind, reflux, or neck tension will arch their back, stiffen, and twist away from the breast, movements that look like sliding but are really an attempt to escape something uncomfortable.
Signs worth watching for:
- Clicking or smacking sounds during sucking
- Nipple pain lasting beyond the first minute
- Visible areola still showing after latch
- Coughing, sputtering, or repeated pulling off
- Back arching, stiffening, or neck twisting
- Frequent need to burp mid-feed
Not every wriggle is a problem. Babies get distracted by noise, light, and their own developing curiosity, especially from around six weeks onward. Distracted squirming tends to come with a relaxed body and a quick return to feeding once you shift somewhere quieter. Pain-driven or flow-driven sliding looks tense and repeats every feed.
How do you position baby to stop them sliding?
Fixing sliding is mostly about geometry. Get the alignment right and baby has no reason to slip.
Bring baby to the breast, not the other way around. Line up ear, shoulder and hip in a straight plane, whole body facing you, tummy to tummy. Hunching yourself forward to reach baby is one of the fastest ways to end up with a shallow latch, because you’re compensating for height instead of fixing position.
Try these holds and checks:
- Cross-cradle hold. Support baby’s neck and shoulders with the hand opposite the feeding breast, not their head. Wait for a wide-open mouth before bringing them on, chin first.
- Football hold. Tuck baby along your side, legs pointing behind you, supported on a pillow at breast height. This one’s useful after a caesarean or for smaller babies who need more head control.
- Laid-back breastfeeding. Recline at roughly 45 degrees with baby tummy-down on your chest. Gravity does the anchoring work here, which helps babies with a fast flow stay latched longer.
- Side-lying. Face baby on the bed, hips stacked, nose level with your nipple. Handy for night feeds, though it takes practice to get the alignment right the first few times.
For each hold, check three things: is baby’s chin buried in the breast, is their nose clear, and does their bottom lip flange outward like a fish rather than tuck in.
A small towel roll under your forearm or behind baby’s back can stop the slow drift that happens over a twenty-minute feed. Tummy-to-mum contact matters more than most parents realise. Any gap between baby’s body and yours becomes leverage for them to twist away.

Pro Tip: If you catch yourself leaning forward to reach baby rather than lifting baby to you, stop and reset. That one habit causes more shallow latches than almost anything else.
How do you manage fast or slow milk flow during feeds?
Flow problems and positioning problems often travel together, but the fixes are different enough to treat separately.
If you have an overactive let-down, baby will typically gulp hard in the first minute, then start coughing, sputtering, or yanking off. Leaning back into a laid-back position lets gravity slow the stream, and letting the first, most forceful spray hit a towel before latching baby on takes the edge off. Breast compressions later in the feed keep milk moving steadily without another gushing letdown catching baby off guard. Managing oversupply and overactive let-down this way tends to reduce the choke-and-pull-off cycle within a feed or two.
Slow flow is the opposite problem: baby works hard for not much reward, gets frustrated, and starts sliding around trying to find a better angle. Breast compressions here do the opposite job, they encourage more milk to move rather than slowing it. Frequent, shorter feeds and skin-to-skin contact between sessions can help supply keep pace with demand.
Bottle-feeding has its own flow rules. Tilt the bottle just enough that milk fills the teat without flooding it, choose a slow-flow teat for younger babies, and pace the feed with breaks every few minutes rather than letting baby drain it in one go. Never prop a bottle and walk away. Paced bottle-feeding technique matters just as much for breastfed babies getting expressed milk as it does for formula feeds.
- Fast flow: lean back, express the first spray, use compressions later in the feed.
- Slow flow: use compressions early and often, feed more frequently, add skin-to-skin time
- Bottles: slow-flow teat, gentle tilt, planned breaks, never propped
When does sliding point to something more than positioning?
Sometimes the fixes above help a little but the sliding never fully resolves. That’s usually a sign to look past technique.
- Tongue-tie. A restricted tongue can’t extend far enough to maintain a deep latch, no matter how well you position baby. A specialist tongue-tie assessment can confirm whether this is contributing.
- Reflux. Frequent spit-up alongside arching and pulling off, especially mid-feed rather than at the end, suggests reflux discomfort rather than a mechanical latch problem.
- Congestion. A blocked nose forces baby to break latch repeatedly just to breathe. Saline drops before a feed sometimes solve this outright.
- Neck tension (torticollis). If baby consistently favours turning to one side and struggles latching on the opposite breast, gentle neck stiffness could be behind it.
If sliding persists past a week of trying different holds, if weight gain is slow, or if pain doesn’t ease, book in with a lactation consultant or your paediatrician. Bring notes on which positions you’ve tried and what happened.
What safety rules matter while you’re troubleshooting?
Never feed baby in a sling or baby carrier. It feels efficient, but it removes your ability to watch baby’s airway and adjust their position the moment something goes wrong. Always hold baby directly for every feed, breast or bottle.
Never prop a bottle against a pillow or cushion and leave baby unattended. NHS safety guidance is unambiguous on this point, propped bottles raise both choking risk and the chance of milk pooling in baby’s mouth.
- Learn to spot the difference between gagging (noisy, baby recovers quickly) and choking (silent, no airflow, needs immediate help)
- Cool expressed milk within an hour of expressing and use or freeze it promptly
- Wash and sterilise bottle parts after every use if you’re combination feeding
Why does posture support actually reduce sliding?
Hunching forward to reach baby is one of the quietest causes of shallow latch, because you compensate for lost height by curling your shoulders, which shortens the distance baby has to travel and shallows the latch in the process. Bringing baby up to breast height, rather than dropping your body down to theirs, keeps the latch deeper and more stable through a whole feed.
When you’re evaluating any nursing support, three things actually matter:
- How much lift it gives (low support forces hunching regardless of how you sit)
- Whether it holds its shape under baby’s weight for a full feed, rather than sagging halfway through
- Whether the base is stable enough that you’re not constantly repositioning it
Pro Tip: Try a support for three or four feeds in a row and count relatch events. If they drop noticeably within the same session, the lift and stability are doing their job.
A quick word on treating feeding as a two-way skill
Sliding is information, not failure. Small experiments, jotting down what worked, and asking for peer or professional support build confidence faster than any single technique.
— Marietjie
Where a properly designed nursing pillow fits in
Everything in this article points back to one mechanical fact: baby needs to come up to you, not the other way around. That’s the entire design brief behind the Zabbidoo Nursing Pillow. Its 18cm lift brings baby to breast height so you’re not hunching to compensate, and the compression-resistant fill holds that height through a full twenty-minute feed instead of sagging by the halfway mark, which is where a lot of cheaper pillows quietly fail you.
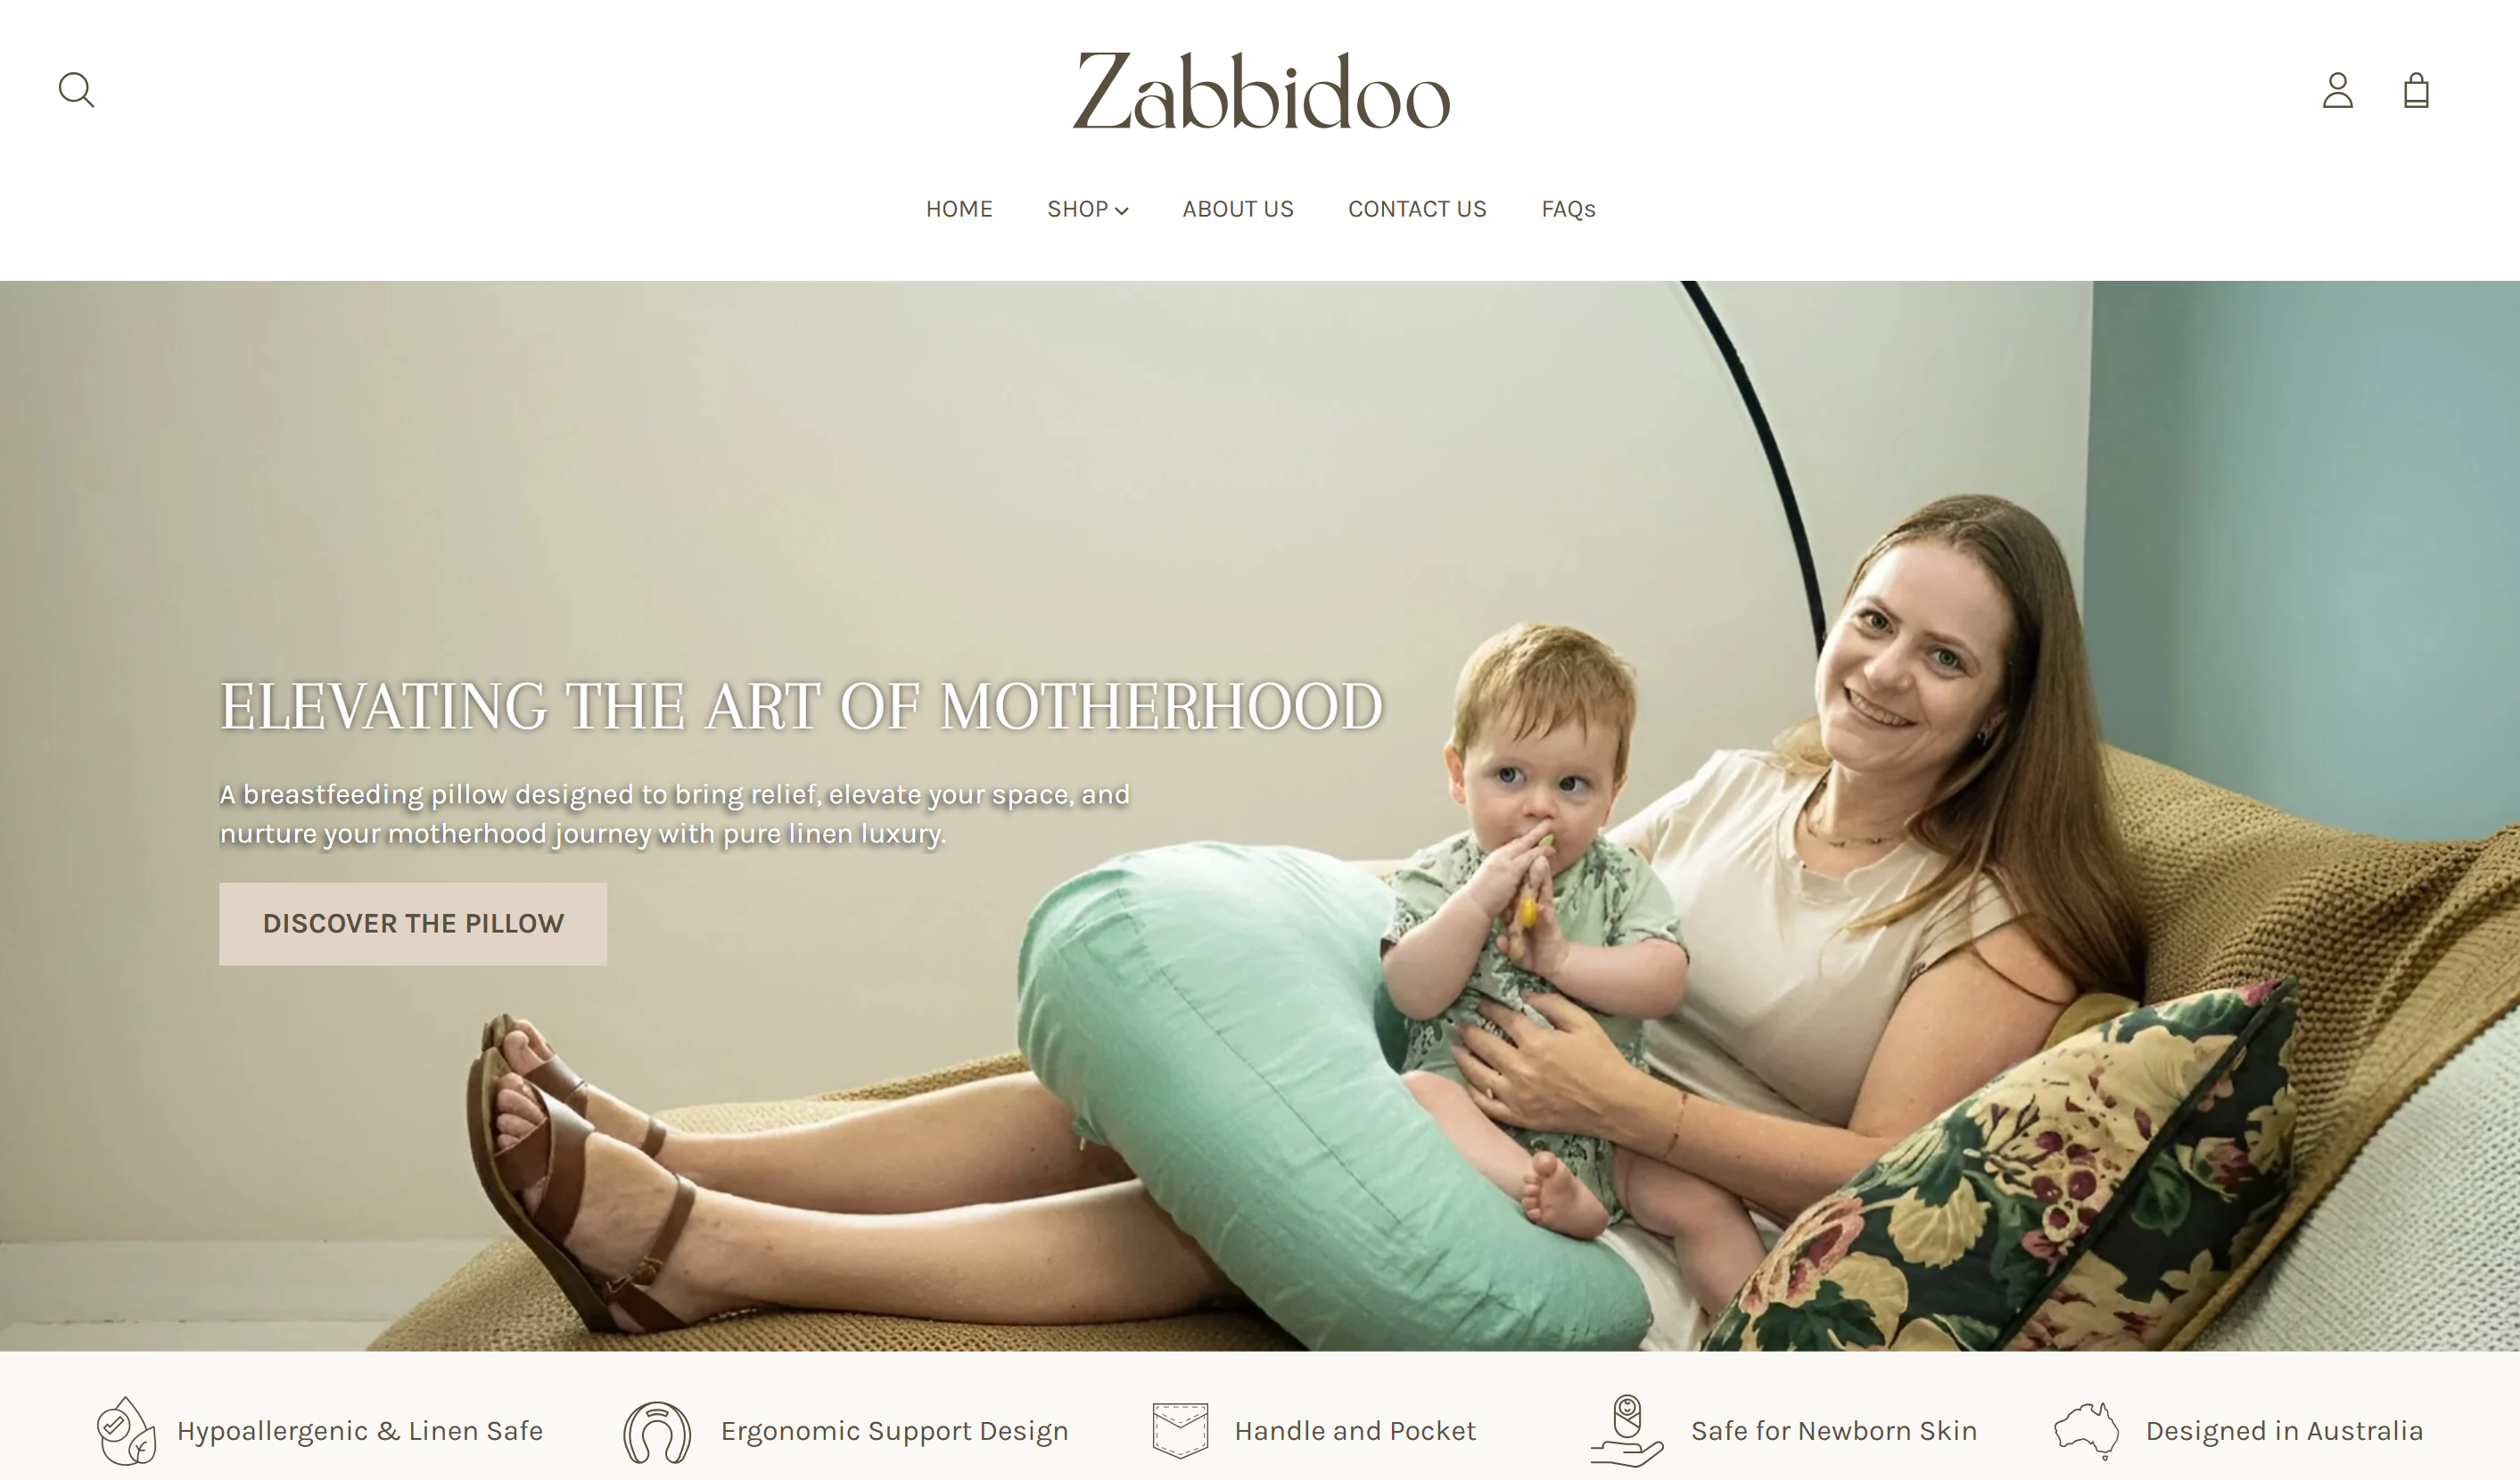
The stable base means less mid-feed repositioning, and a breathable cover stays comfortable through multiple daily feeds. If you’re mid-troubleshooting, try it for a few feeds and count relatch events the same way you’d track any other fix. Many parents notice fewer slips and less shoulder strain after trying a support with adequate lift and stability. You can check the full feature rundown on the Nursing Pillow product page or see the range at Zabbidoo and order directly for a one-off price.
Where to read more
For deeper detail, the Australian Breastfeeding Association covers attachment and latch, La Leche League International explains oversupply management, and NHS sets out feeding safety basics. For a professional feeding assessment, lactation counselling services can help pinpoint issues home fixes can’t solve.
Sources
- Baby-led attachment — Australian Breastfeeding Association
- Breast milk oversupply and overactive milk ejection reflex — La Leche League International
- Baby and toddler safety — NHS
FAQ
Why does my baby squirm and unlatch while breastfeeding?
Squirming and unlatching usually means a shallow latch, a too-fast let-down, or discomfort from wind or reflux. Check alignment first, ear, shoulder and hip in a line, before troubleshooting further.
Why is my baby so fidgety during feeds?
Fidgeting can be normal distraction from around six weeks, but frequent tense fidgeting alongside arching or coughing points to flow or latch problems rather than curiosity.
Why does my baby squirm and twist during bottle feeds?
Twisting during bottle feeds often means the flow is too fast for baby to manage comfortably. Switch to a slower-flow teat and pace the feed with regular breaks.
What are some signs of unusual movement in babies during feeds?
Repetitive arching, stiffening, or one-sided head turning during every feed is worth mentioning to your paediatrician, particularly if it doesn’t ease with position changes, since it can sometimes reflect neck tension or a developmental concern.
Can a nursing pillow actually stop my baby sliding?
A pillow with real lift and a stable, non-collapsing base can reduce hunching and repositioning during feeds. The Zabbidoo Nursing Pillow is built around that 18cm lift specifically to bring baby to breast height rather than the reverse.