

Upright holds are the most effective reflux feeding positions to start with. Hold your baby with their head above their tummy, feed in an upright or semi-upright angle, then keep them upright for 20–30 minutes after the feed. Three positions worth trying straight away are:
- Upright over-shoulder hold: baby chest-to-chest with you, head resting on your shoulder, body angled at roughly 45–90°.
- Laid-back (reclined) feeding: you recline at about 45°, baby lies tummy-down on your chest, gravity keeps them settled against you.
- Diagonal cradle or football hold: baby’s head is higher than their bottom throughout the feed, with their body angled across or beside you.
Two quick wins alongside positioning: offer smaller, more frequent feeds rather than large volumes, and burp every 30–60 mL (roughly every 1–2 ounces). If you are bottle-feeding, check the nipple flow — too fast a flow causes gulping and swallowed air, both of which worsen reflux. Read on for step-by-step instructions, equipment tips, and the signs that tell you when a position is actually working.
Key takeaways
Upright feeding positions combined with after-feed holding and paced feeding are the most effective conservative measures for reducing infant reflux symptoms.
| Point | Details |
|---|---|
| Start upright | Use the over-shoulder or koala hold to keep baby’s head above their tummy during feeds. |
| Hold upright after feeds | Keep baby upright for 20–30 minutes after each feed; avoid car seats and bouncers. |
| Burp mid-feed | Burp every 30–60 mL during the feed, not only at the end, to reduce swallowed air. |
| Check nipple flow | Use the slowest available flow; thicken formula only on paediatrician advice. |
| Sleep flat on back | Always place baby on their back on a flat mattress for sleep — no inclined surfaces. |
| Zabbidoo nursing pillow | The 18 cm lift and compression-resistant design supports consistent feeding angles for reflux-friendly holds. |
Table of Contents
- Why the right reflux feeding position reduces symptoms
- Step-by-step: the best feeding positions for reflux
- Bottle-feeding technique: pacing, nipple flow, and thickening
- Equipment that supports reflux-friendly holds
- After-feed routines: upright time, burping, and safe sleep transitions
- Red flags: when to call your GP or paediatrician
- Common questions about reflux and feeding positions
- What actually works: a practical perspective
- The Zabbidoo nursing pillow supports reflux-friendly holds
- Useful Australian and clinician resources
- Sources
Why the right reflux feeding position reduces symptoms
Gravity is doing most of the work here. When a baby’s head sits higher than their stomach during a feed, milk is less likely to travel back up the oesophagus. Infants have an immature lower oesophageal sphincter — the valve between the stomach and the food pipe — which means it relaxes and opens more easily than it does in older children. Positioning does not fix that immaturity, but it uses gravity to compensate for it, which is why it sits at the top of conservative care recommendations.
Research suggests that upright positioning may reduce reflux-related respiratory symptoms even when it does not eliminate every reflux event. So if your baby still spits up occasionally in an upright hold, that is normal. What you are watching for is less coughing during feeds, less arching of the back, calmer swallowing, and a more settled baby in the 20–30 minutes after eating.
Step-by-step: the best feeding positions for reflux
These holds work for both breastfeeding and bottle-feeding. Each one keeps the baby’s head higher than their tummy, which is the core principle. For a visual walkthrough of each hold, the infant feeding positions guide from Zabbidoo covers body placement with photos.

1. Upright over-shoulder hold
Why try it: Keeps baby almost vertical, giving gravity maximum advantage.
- Sit upright in a supportive chair.
- Hold baby chest-to-chest, their chin over your shoulder.
- Support their bottom with one hand and their back with the other.
- Keep their airway visible — you should be able to see their face in a mirror or by turning your head.
- Feed at the breast or with a bottle angled slightly downward so milk fills only the nipple tip.
Pro Tip: Place a flat hand between baby’s chest and yours to feel their breathing rhythm. If swallowing speeds up or they start gulping, pause and let them settle before continuing.
Safety: never use this as a sleep position. Always supervise and keep the airway clear.
2. Laid-back (biological nurturing) position
Why try it: Your reclined body supports the baby’s whole front, reducing their effort and slowing the feed naturally.
- Recline in a chair or on a bed at roughly 45°.
- Lay baby tummy-down on your chest, their head at breast level.
- Let their legs straddle your body or rest to one side.
- Their weight rests on you — no need to hold them tightly.
- Guide the latch or bottle from below, keeping the head slightly higher than the hips.
La Leche League recommends this position alongside the diagonal cradle for babies with reflux, noting it keeps the head above the tummy throughout.
Signs it is helping: baby feeds more slowly, swallows quietly, and does not pull off repeatedly.
3. Diagonal cradle or football hold
Why try it: Gives you control over baby’s head angle and keeps their body on a diagonal rather than flat.
- Cradle baby across your body at a diagonal, head at your elbow, bottom lower than the head.
- For the football hold, tuck baby under your arm like a rugby ball, their legs pointing behind you, head at your hand.
- In both holds, baby’s head should be higher than their stomach.
- Support the jaw gently with your thumb and forefinger if needed to maintain a good latch.
Pro Tip: If baby keeps unlatching or arching, try shifting the angle by 10–15° and check that their ear, shoulder, and hip are in a straight line.
Troubleshooting: if arching continues, try the upright over-shoulder hold instead — some babies with significant reflux do better with a more vertical angle.
4. Koala (straddle) hold
Why try it: Baby sits upright straddling your thigh, spine straight, head above stomach — one of the most vertical positions available.
- Sit baby facing you, one leg either side of your thigh.
- Support their back and head with both hands.
- Bring them to the breast or bottle at chest height rather than leaning down to them.
- Keep their spine gently upright, not slumped.
This hold works particularly well for older babies with good head control. For newborns, extra head support is needed throughout.
5. Elevated side-lying bottle hold
Why try it: Mimics the natural alignment of breastfeeding and lets baby pace the feed.
The NHS elevated side-lying method places baby on their left side with head and trunk elevated to approximately 45–60°, supported by folded towels. This position reduces vomiting for some infants by slowing the feed and reducing gastric pressure.
- Lay baby on their left side on a firm, flat surface.
- Use folded towels to elevate the head and trunk to 45–60°.
- Offer the bottle at a gentle angle so milk fills only the teat.
- Stay with baby throughout — never leave them unattended in this position.
Safety: this is a supervised feeding position only, not a sleep position.
Bottle-feeding technique: pacing, nipple flow, and thickening
Paced bottle-feeding is the single most useful adjustment for bottle-fed babies with reflux. It slows the feed, reduces air swallowing, and lets baby control the pace. Hold baby in a semi-upright position (roughly 45°), offer the bottle horizontally so milk barely reaches the teat, and allow baby to draw the milk themselves rather than having it flow freely.

Nipple flow matters. A nipple that flows too fast overwhelms the baby’s suck-swallow-breathe cycle, causing gulping and excess air intake. Start with the slowest flow available for your baby’s age and only move up if they are working very hard to feed.
Pro Tip: Watch for these cues that the flow is too fast: milk dribbling from the corners of the mouth, rapid swallowing, wide eyes, or pulling off the teat. Pause the feed, hold baby upright for 20–30 seconds, then resume.
For some infants, clinicians recommend thickening formula. The MSD Manual advises that rice cereal at 1–3 teaspoons (approximately 5–15 mL) per 30 mL of formula can reduce regurgitation, and that a larger or cross-cut nipple is usually needed to maintain flow. Only thicken formula on a paediatrician’s advice — changing formula composition without guidance can affect nutrition.
| Adjustment | Guidance | Note |
|---|---|---|
| Nipple flow | Start at slowest available | Move up only if baby struggles |
| Thickening (rice cereal) | 1–3 tsp (5–15 mL) per 30 mL formula | Paediatrician advice required |
| Nipple orifice | Enlarge or cross-cut when thickening | Prevents frustration and excess air |
| Burping interval | Every 30–60 mL (1–2 oz) | More frequent if baby is gassy |
Equipment that supports reflux-friendly holds
A nursing pillow designed with adequate lift does two things at once: it brings baby up to the correct height for the hold, and it reduces the carer’s need to lean forward. That forward lean is what causes the neck and lower back strain that makes long feeds exhausting — and an exhausted carer repositions more, which disrupts the feed.
When choosing a nursing pillow for reflux, look for:
- Adequate lift: at least 15–18 cm to bring baby to breast or bottle height without you hunching.
- Compression resistance: a pillow that collapses under baby’s weight defeats the purpose. Firm, shape-retaining fill keeps the angle consistent throughout the feed.
- Stable base: the pillow should not slide on your lap or the chair.
- Breathable cover: babies with reflux often feed for longer periods; a breathable, washable cover matters for hygiene and comfort.
- Easy cleaning: spit-up is a given. Machine-washable components save time.
Pro Tip: Use the pillow to support the football or diagonal cradle hold by resting baby’s body along the pillow while you guide the head with your hand. This frees one hand for burping without losing the angle.
Safety rules for aids: do not prop baby on a pillow and leave them unattended. Car seats and bouncers are not suitable substitutes for upright holding after a feed — Mayo Clinic notes that seated devices increase gastric pressure and can worsen reflux rather than help it. Use shoulder holds or the koala hold for after-feed upright time instead.
After-feed routines: upright time, burping, and safe sleep transitions
Keep baby upright and non-seated for a duration that allows gravity to help keep stomach contents down after every feed. Mayo Clinic recommends holding infants in an upright or semi-upright position for around 30 minutes after feeding so gravity keeps stomach contents down. La Leche League suggests 15–20 minutes as a minimum. The practical target is 20–30 minutes where your schedule allows.
Burping technique: burp gently over the shoulder or in a sitting position on your lap, supporting the chin. Aim to burp every 30–60 mL during the feed, not just at the end.
| After-feed step | Timing | Method |
|---|---|---|
| Upright hold | 20–30 minutes | Over shoulder or koala hold — not car seat |
| Burping | Every 30–60 mL during feed | Over shoulder or sitting on lap |
| Settling | After upright time | Lay flat on back on firm mattress |
Safe sleep transition: once upright time is done, place baby on their back on a flat, firm mattress. Do not tilt the cot mattress or use wedges — Nationwide Children’s guidance confirms that raising the head of the cot is not recommended. Never leave baby to sleep in a car seat, bouncer, or swing after a feed, even if they have fallen asleep there.
- Always place baby on their back for sleep, regardless of reflux.
- Never use a propped or inclined sleep surface.
- Positioning changes apply to feeding and awake upright time only — not sleep.
Red flags: when to call your GP or paediatrician
Most reflux in infants is normal and improves with positioning and feeding adjustments. These signs need prompt medical review:
- Poor weight gain or weight loss between check-ups.
- Projectile vomiting — forceful enough to land well away from baby.
- Blood in vomit or vomit that looks like coffee grounds.
- Persistent feeding refusal across multiple feeds.
- Difficulty breathing, noisy breathing, or colour changes during or after feeds.
- Extreme, inconsolable irritability that does not settle with any usual measure.
- Choking or gagging regularly during feeds.
When you call, tell the clinician: how often baby feeds, approximate volume per feed, how many times per day they vomit, and whether weight gain has been normal at recent checks. For breathing difficulty or colour changes, seek emergency care immediately.
The Raising Children Network and the Royal Children’s Hospital Melbourne both provide parent-facing guidance on when reflux needs clinical assessment — both are worth bookmarking.
Common questions about reflux and feeding positions
Does upright feeding stop all spitting up? Not always. Reduced coughing and calmer feeds are the signs to watch for.
Is side-lying safe for a baby with reflux? Only as a supervised feeding position, not for sleep. The elevated left-side-lying bottle hold described above is clinician-endorsed for feeding, but baby must always be placed on their back on a flat surface for sleep.
Can a poor latch cause reflux symptoms? Yes. A shallow latch causes excess air swallowing, which increases gastric pressure and worsens regurgitation. If latch is an issue, contact the Australian Breastfeeding Association for support.
Are breastfed babies less likely to have reflux? Breastfed babies tend to have shorter, more frequent feeds, which can reduce reflux episodes — but reflux occurs in both breastfed and formula-fed infants. Positioning matters regardless of feeding method.
Will burping always help? Burping reduces swallowed air and is consistently recommended, but it does not address the underlying sphincter immaturity. It works best as part of a broader routine: smaller feeds, correct positioning, and upright time after.
What actually works: a practical perspective
The advice that gets lost in most reflux articles is this: position is only half the equation. The other half is carer comfort. A hold you cannot sustain for 15 minutes because your back is screaming is not actually helping your baby — you will shift, they will shift, and the angle you worked to achieve is gone.
Start with the upright over-shoulder hold for the first few weeks, then try laid-back feeding once you are both more confident. Use a firm, height-adequate pillow to support the diagonal cradle or football hold so your arms are not doing all the work. Check your own posture — signs of poor feeding posture show up as neck tension and wrist fatigue within the first few weeks.
Three quick tips worth keeping:
- Set a timer for upright time after feeds. Twenty minutes feels long when you are sleep-deprived; a timer removes the guesswork.
- Burp mid-feed, not just at the end. Most of the air that causes discomfort enters in the first half of the feed.
- If a position is not working after three or four feeds, try the next one on the list rather than persisting. Babies respond differently, and there is no single correct hold.
The Zabbidoo nursing pillow supports reflux-friendly holds
A higher-lift nursing pillow changes the geometry of every hold on this list. Instead of leaning down to baby, baby comes up to you — which keeps the feeding angle consistent and reduces the repositioning that breaks a good latch or disrupts an upright hold mid-feed.
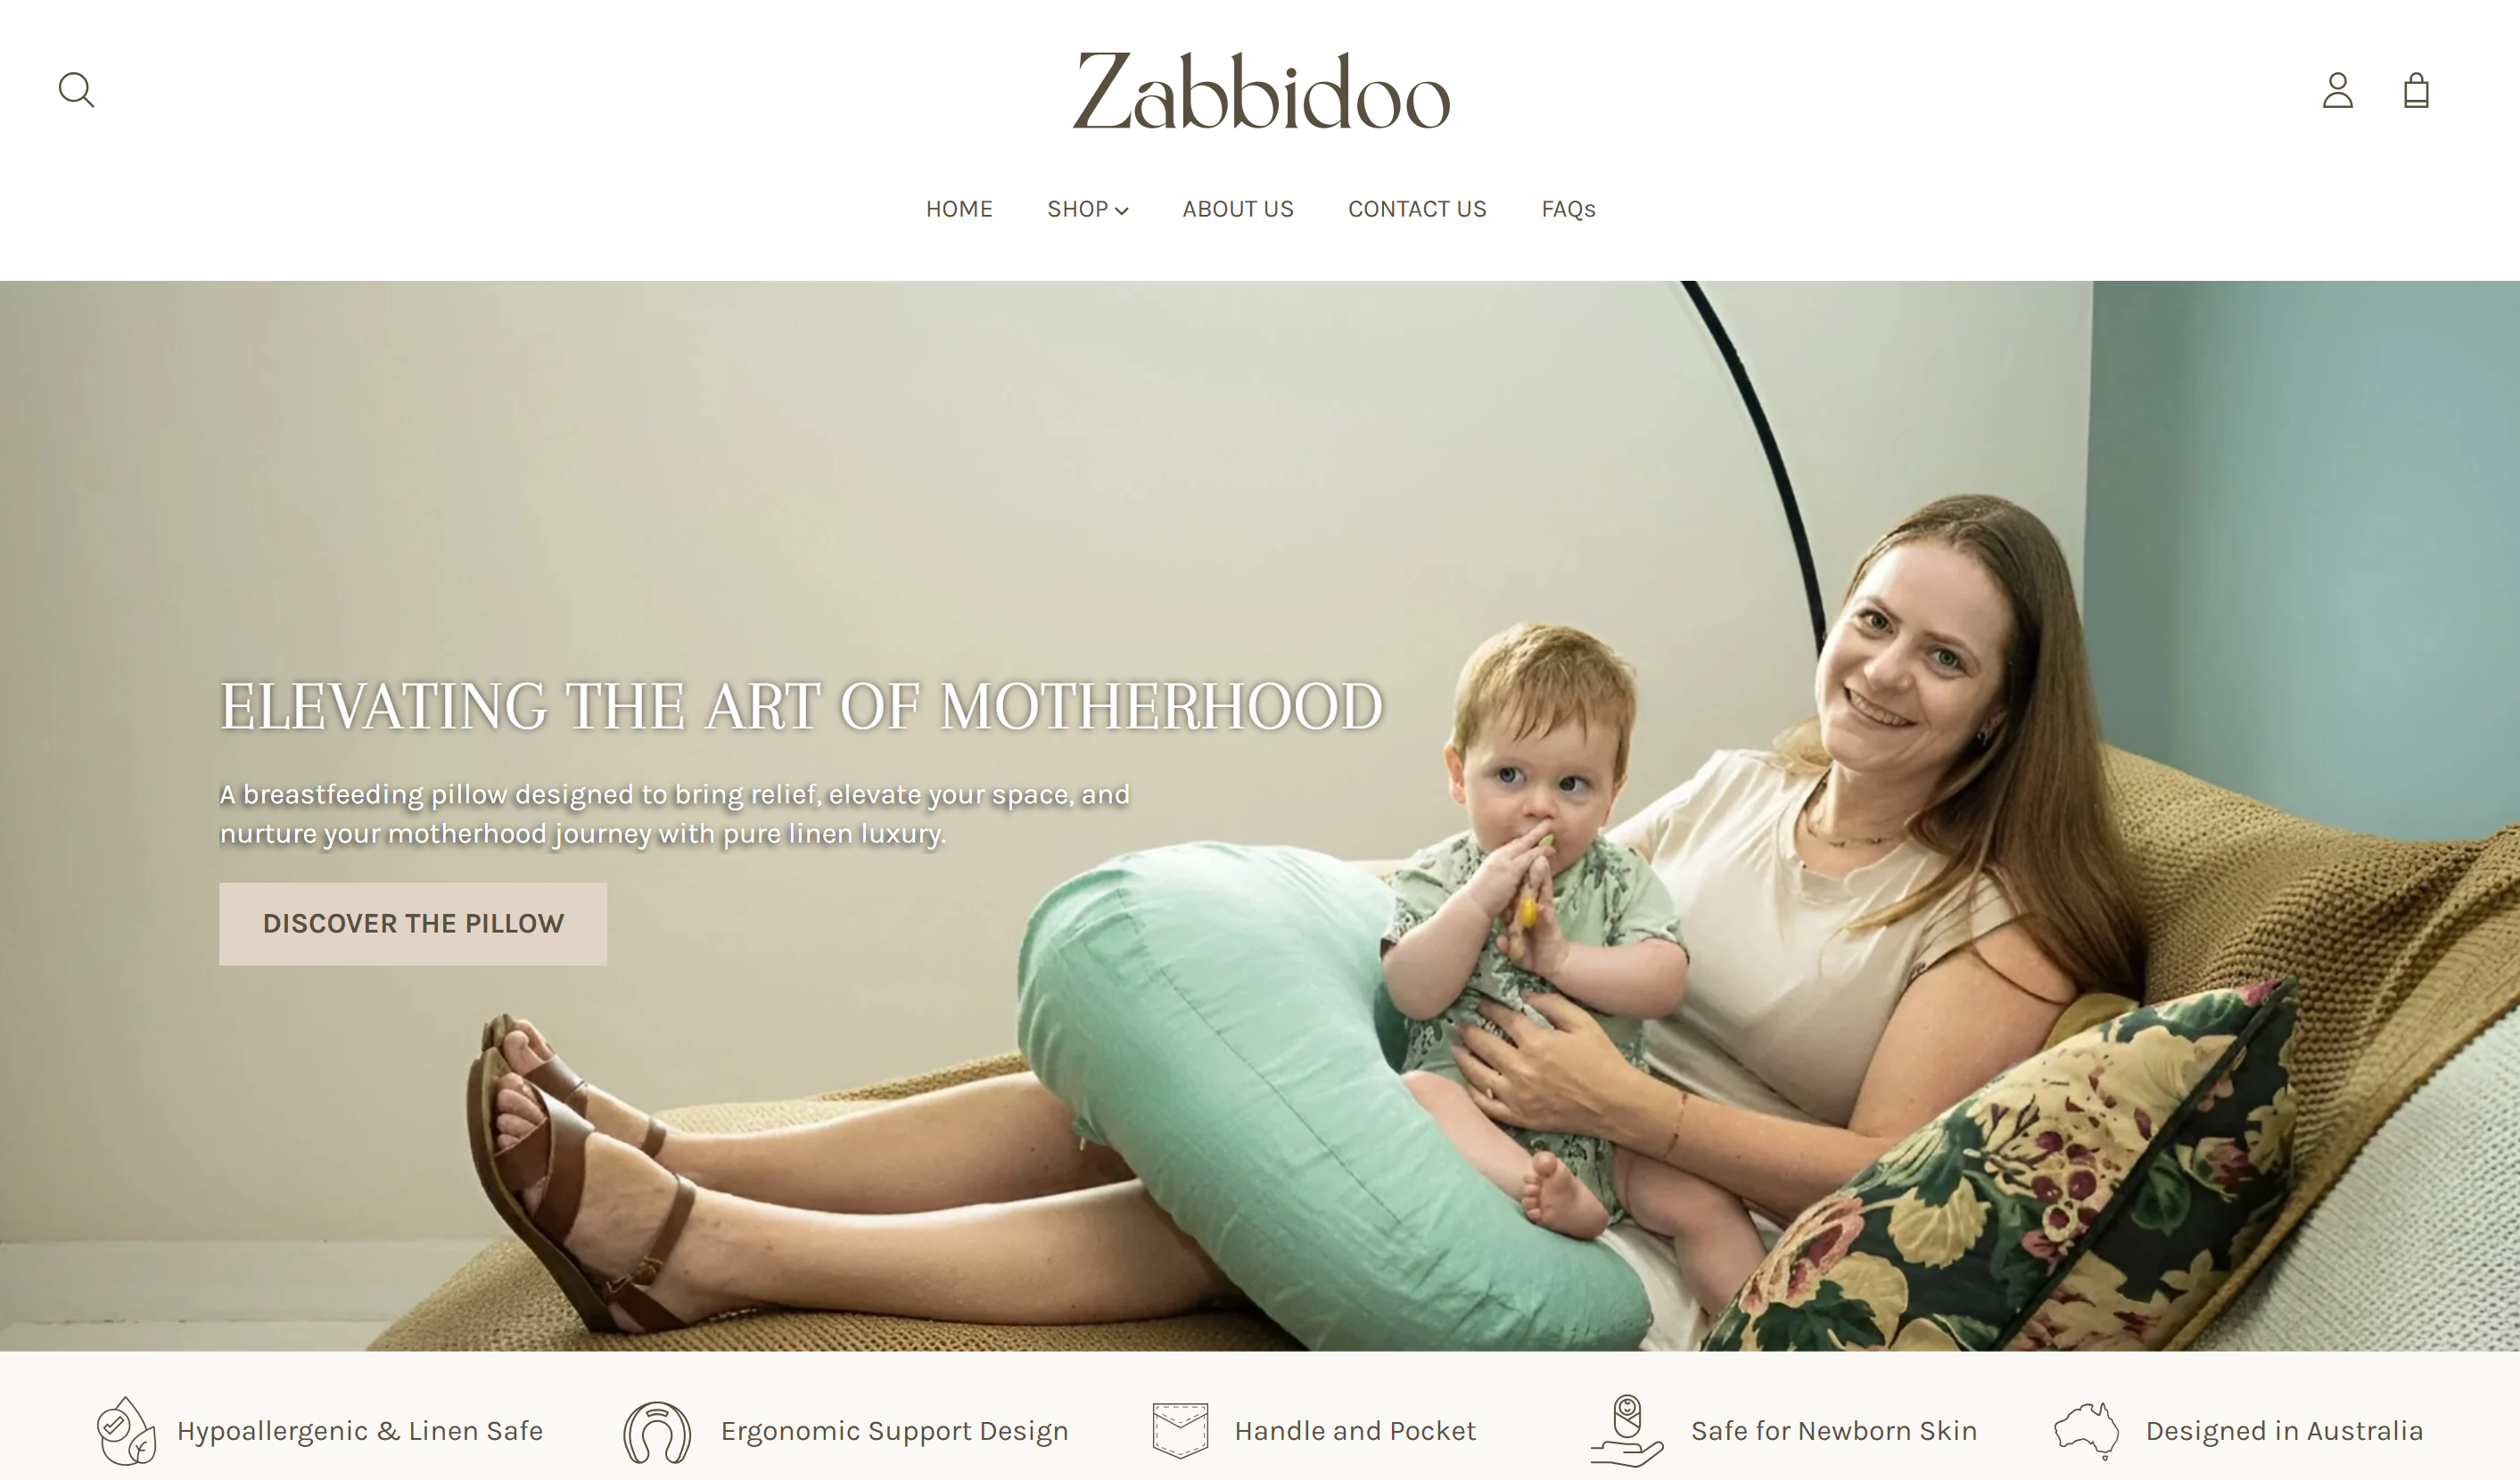
The Zabbidoo nursing pillow is built with an 18 cm lift, high compression resistance so it holds its shape under baby’s weight throughout the feed, and a breathable French flax linen cover that is machine washable. The stability-focused design means it stays in place on your lap during the football hold, the diagonal cradle, and the koala hold — the three positions most useful for reflux. A built-in pocket and portable handle make it practical for feeds away from home.
One honest note: the Zabbidoo pillow supports positioning and carer comfort. It is not a medical device and is not a treatment for reflux. For persistent or severe symptoms, see your paediatrician. For everything else — the daily work of feeding a baby with reflux comfortably — it is worth having a pillow that does not collapse halfway through.
View the Zabbidoo nursing pillow and check current availability at zabbidoo.com/products/nursing-pillow.
Useful Australian and clinician resources
- Australian Breastfeeding Association — breastfeeding support, latch guidance, and local lactation consultants across Australia.
- Raising Children Network — evidence-based parent guidance on reflux, feeding, and infant development, written for Australian families.
- Royal Children’s Hospital Melbourne — Clinical Practice Guidelines — clinician-level guidance on GORD in infants, including when to refer and treatment thresholds.
- Mayo Clinic: Infant acid reflux — clear treatment and positioning advice from a major clinical institution (US-based; principles apply broadly).
- La Leche League International: Reflux — breastfeeding-specific positioning tips and after-feed routines for babies with reflux.
- MSD Manual: Gastroesophageal reflux in infants — consumer-facing clinical overview including thickening guidance and conservative care steps.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Gastroesophageal reflux in infants - Children’s Health - MSD Manual Consumer Version
- Infant acid reflux - Diagnosis and treatment - Mayo Clinic
- Bottle feeding your baby
- Reflux - La Leche League International
- The Efficacy of the Upright Position on Gastro-Esophageal Reflux and …