

Continuous sharp or pinching pain while your baby nurses is not normal, so stop, break the latch safely and try a quick reposition before continuing. Fleeting tenderness in the first days can be ordinary, but pain that persists through a feed or worsens usually signals a fixable problem with the latch. Reposition your baby so their nose sits level with your nipple, and if pain continues past a minute or two, or you notice fever, redness or cracked skin, get help from a lactation consultant or your GP.
TL;DR:
- Persistent, sharp nipple pain during breastfeeding often indicates a mechanical latch issue or underlying medical condition requiring professional assessment.
- Proper positioning, with the baby’s nose level with the nipple and supported at a suitable height, can significantly reduce latch-related soreness.
- Signs such as cracked or bleeding nipples, clicking sounds, or a shallow latch during feeding point to needed adjustments or diagnoses like tongue tie or thrush.
- Avoid aggressive pumping, vigorous massage, or forcing a poor latch, as these can worsen inflammation and pain rather than alleviate symptoms.
- Using a supportive pillow that maintains breast height and promotes correct posture can improve latch efficiency and reduce nipple trauma.
Table of Contents
- Normal soreness or a problem latch: how to tell the difference
- What actually causes painful latching
- Relieving pain and protecting damaged nipples right now
- Positioning and latch fixes to try right now
- Medical causes and red flags that need urgent attention
- When to get professional help and what happens next
- What the evidence says about posture and ergonomic support
- The real problem is rarely just “a bad latch”
- Zabbidoo nursing pillow: a posture-first support for painful feeds
- FAQ
- Sources
Normal soreness or a problem latch: how to tell the difference
Some tenderness in the first week or two, especially right as your baby attaches, is common and usually fades within the first 30 to 60 seconds of a feed. Pain that stays sharp, stabbing or burning throughout a feed is a different story, and it almost always means something mechanical needs adjusting.
Physical clues after a feed tell you a lot. Check for these signs once your baby comes off the breast:
- A white or pink line pressed across the tip of your nipple, or a flattened, wedge-shaped nipple
- Cracks, blisters or visible bleeding on the nipple surface
- Ongoing soreness that lasts well after the feed has finished, rather than easing within seconds
During the feed itself, listen and watch closely. A clicking sound, no audible swallowing, or a baby who seems to be clamping or gumming rather than drawing deeply are all signs the latch is too shallow. Poor latch or attachment is the most frequent cause of nipple pain, and persistent pain is often the result of several overlapping factors rather than one single cause.
What actually causes painful latching
Most painful latches come down to mechanics, though medical and infant-anatomy factors play a role too. Getting a sense of which bucket your situation falls into helps you know what to try first.
- Mechanical issues: a shallow latch, a baby positioned too low on the breast, or a mother hunching forward to bring the breast down to the baby instead of bringing the baby up
- Infant anatomy: tongue tie or a high, narrow palate can make it physically harder for a baby to draw enough breast tissue into their mouth, leading to biting or gumming motions
- Medical causes: thrush, nipple dermatitis, engorgement, or early ductal inflammation that can progress toward mastitis if untreated
- Pumping habits: an incorrectly sized flange or excessive pumping can irritate nipple tissue independently of breastfeeding itself, and postpartum fluid retention can temporarily change breast shape and make early positioning trickier
The Australian Breastfeeding Association notes that poor attachment is the most common cause of sore nipples, which is worth remembering before assuming something more serious is going on. That said, persistent or severe pain deserves a proper look rather than guesswork, since mechanical and medical causes often need different fixes.
Relieving pain and protecting damaged nipples right now
If a feed has already become painful, there’s a right way to stop it and a few things you can do before trying again.
- Slide a clean finger into the corner of your baby’s mouth to break the suction before pulling away, rather than pulling the breast out while they’re still latched.
- Try reverse pressure softening: gently press fingertips around the base of the nipple for 30 to 60 seconds to soften swollen tissue before relatching.
- Hand express a few drops of milk to soften the nipple tip and make it easier for your baby to draw in a fuller mouthful on the next attempt.
- Relatch aiming for a wider, deeper mouthful, with your baby’s chin and lower jaw making contact first.
Afterwards, a few simple measures can ease symptoms without masking a problem that needs fixing. A smear of your own expressed breastmilk left to air dry, a cool compress for short bursts, and paracetamol or an NSAID at the usual adult dose can all help manage discomfort in the meantime.
Pro Tip: Avoid leaving thick, occlusive ointments on the nipple for extended periods between feeds, since trapped moisture can slow healing rather than speed it.
What to skip: aggressive pumping to try to “fix” supply or drainage, vigorous massage of sore or inflamed tissue, and repeated attempts to force a latch that clearly isn’t working. Clinical protocol guidance cautions that aggressive pumping or massage aimed at “emptying” the breast can increase swelling and worsen pain rather than help, so gentler, smaller interventions are usually the better choice.
Positioning and latch fixes to try right now
Most latch pain traces back to positioning, and small adjustments often make an immediate difference. Bring your baby to the breast rather than leaning or hunching down to them: chest to chest, nose level with the nipple, and supported at a height where you can sit upright.
Different holds suit different situations:
- Cross-cradle hold gives you the most control over your baby’s head, useful in the early weeks while you’re both learning
- Laid-back hold lets gravity help your baby open wide and self-attach, often easing a shallow latch
- Side-lying hold takes pressure off a healing caesarean scar or tired arms during night feeds
A firm, stable support under your baby, whether that’s a folded towel, firm cushions, or a dedicated nursing pillow, keeps them at the right height so you’re not compensating with your neck or shoulders. For more detail on setting this up quickly, our guide to common posture mistakes and a one-minute setup walks through the adjustments step by step, and our positioning fixes for nipple pain covers quick troubleshooting during a feed.
Pro Tip: Rate your pain on a 1 to 10 scale at the start of each feed. If the number consistently drops over a few days alongside fewer compression marks and audible swallowing, you’re on the right track.
Medical causes and red flags that need urgent attention
Some causes of latch pain need medical assessment rather than a positioning fix. Fever, spreading redness on the breast, a firm or tender lump, or pain that’s sharply worse in one specific spot are all signs that warrant prompt attention.
- Thrush typically causes burning pain deep in the breast along with pink, shiny or flaky nipple skin, sometimes alongside white patches in your baby’s mouth
- Dermatitis tends to cause itching and flaking without the deep burning sensation
- Mastitis or ductal inflammation often brings flu-like symptoms, localised redness and a tender, warm patch of breast tissue
About 1 in 10 breastfeeding mothers experience nipple or breast pain unrelated to mastitis, underlining why persistent pain deserves proper diagnosis rather than assumptions. HealthDirect advises seeing a doctor early for mastitis symptoms such as fever, chills or spreading redness, and notes that continuing to breastfeed or express is generally safe and helpful rather than something to avoid.
When to get professional help and what happens next
If pain persists beyond simple positioning fixes, or any red flags appear, reach out sooner rather than later. An Australian Breastfeeding Association counsellor, an IBCLC lactation consultant, your child health nurse or GP can all help, depending on severity.
- For latch and positioning concerns: an IBCLC or ABA counsellor can observe a full feed and spot issues you can’t see yourself
- For suspected infection or systemic symptoms: your GP can assess for mastitis, thrush or other medical causes
- For suspected tongue tie or anatomical issues: a referral for assessment, and possibly frenotomy, may follow
Before an appointment, jot down when pain occurs, how long it lasts, and any photos of nipple damage. A lactation consultation typically involves a full feeding observation alongside a check of your baby’s oral anatomy, so expect practical coaching rather than a quick fix.
What the evidence says about posture and ergonomic support
Clinical guidance consistently points to one underlying principle: fixing the fit and hold between baby and breast resolves most pain at its source. Clinical reviews identify mechanical micro-trauma from repetitive, uneven forces during suckling as the leading cause of nipple pain, recommending that clinicians focus on eliminating those conflicting forces rather than treating the surface damage alone.
- Bringing baby to breast height, rather than leaning down to them, reduces the hunching that often produces a shallow, poorly angled latch
- A stable, elevated support can help maintain that height consistently across a feed, particularly during the newborn weeks when arms tire quickly
Pro Tip: Think of positioning support as something that holds your progress steady between lactation consultant visits, not a replacement for a proper feeding assessment.
A firm nursing pillow that keeps its shape under weight, rather than one that flattens within minutes, makes this kind of sustained support realistic to maintain through a full feed.

The real problem is rarely just “a bad latch”
The advice to “just fix the latch” gets repeated so often that it starts to sound like a cliché, which undersells how much skill and observation it actually takes to diagnose correctly. A shallow latch, tongue tie, thrush and simple fatigue-driven poor posture can all produce similar pain, and guessing wrong wastes days you don’t get back in a newborn’s first weeks.

What’s underrated is how much posture alone contributes, independent of anything happening in your baby’s mouth. Mothers are routinely told to watch for a wide mouth and flared lips, and far less often told that hunching forward for twenty minutes, eight times a day, will produce its own pain regardless of latch quality. Fix your own position first. It’s the fastest, lowest-risk change available, and it costs you nothing to try before booking an appointment.
If pain hasn’t eased within a few days of genuine effort on positioning, that’s the signal to stop experimenting alone and get a proper assessment. Persistent guesswork helps no one, least of all a baby who needs you rested and willing to keep feeding.
— Marietjie
Zabbidoo nursing pillow: a posture-first support for painful feeds
A pillow that collapses under your baby’s weight forces you right back into the hunch that causes shallow latches in the first place. Our Nursing Pillow is built with an 18cm lift that brings your baby up to breast height instead of you leaning down, plus a compression-resistant fill that holds its shape feed after feed rather than flattening within minutes.
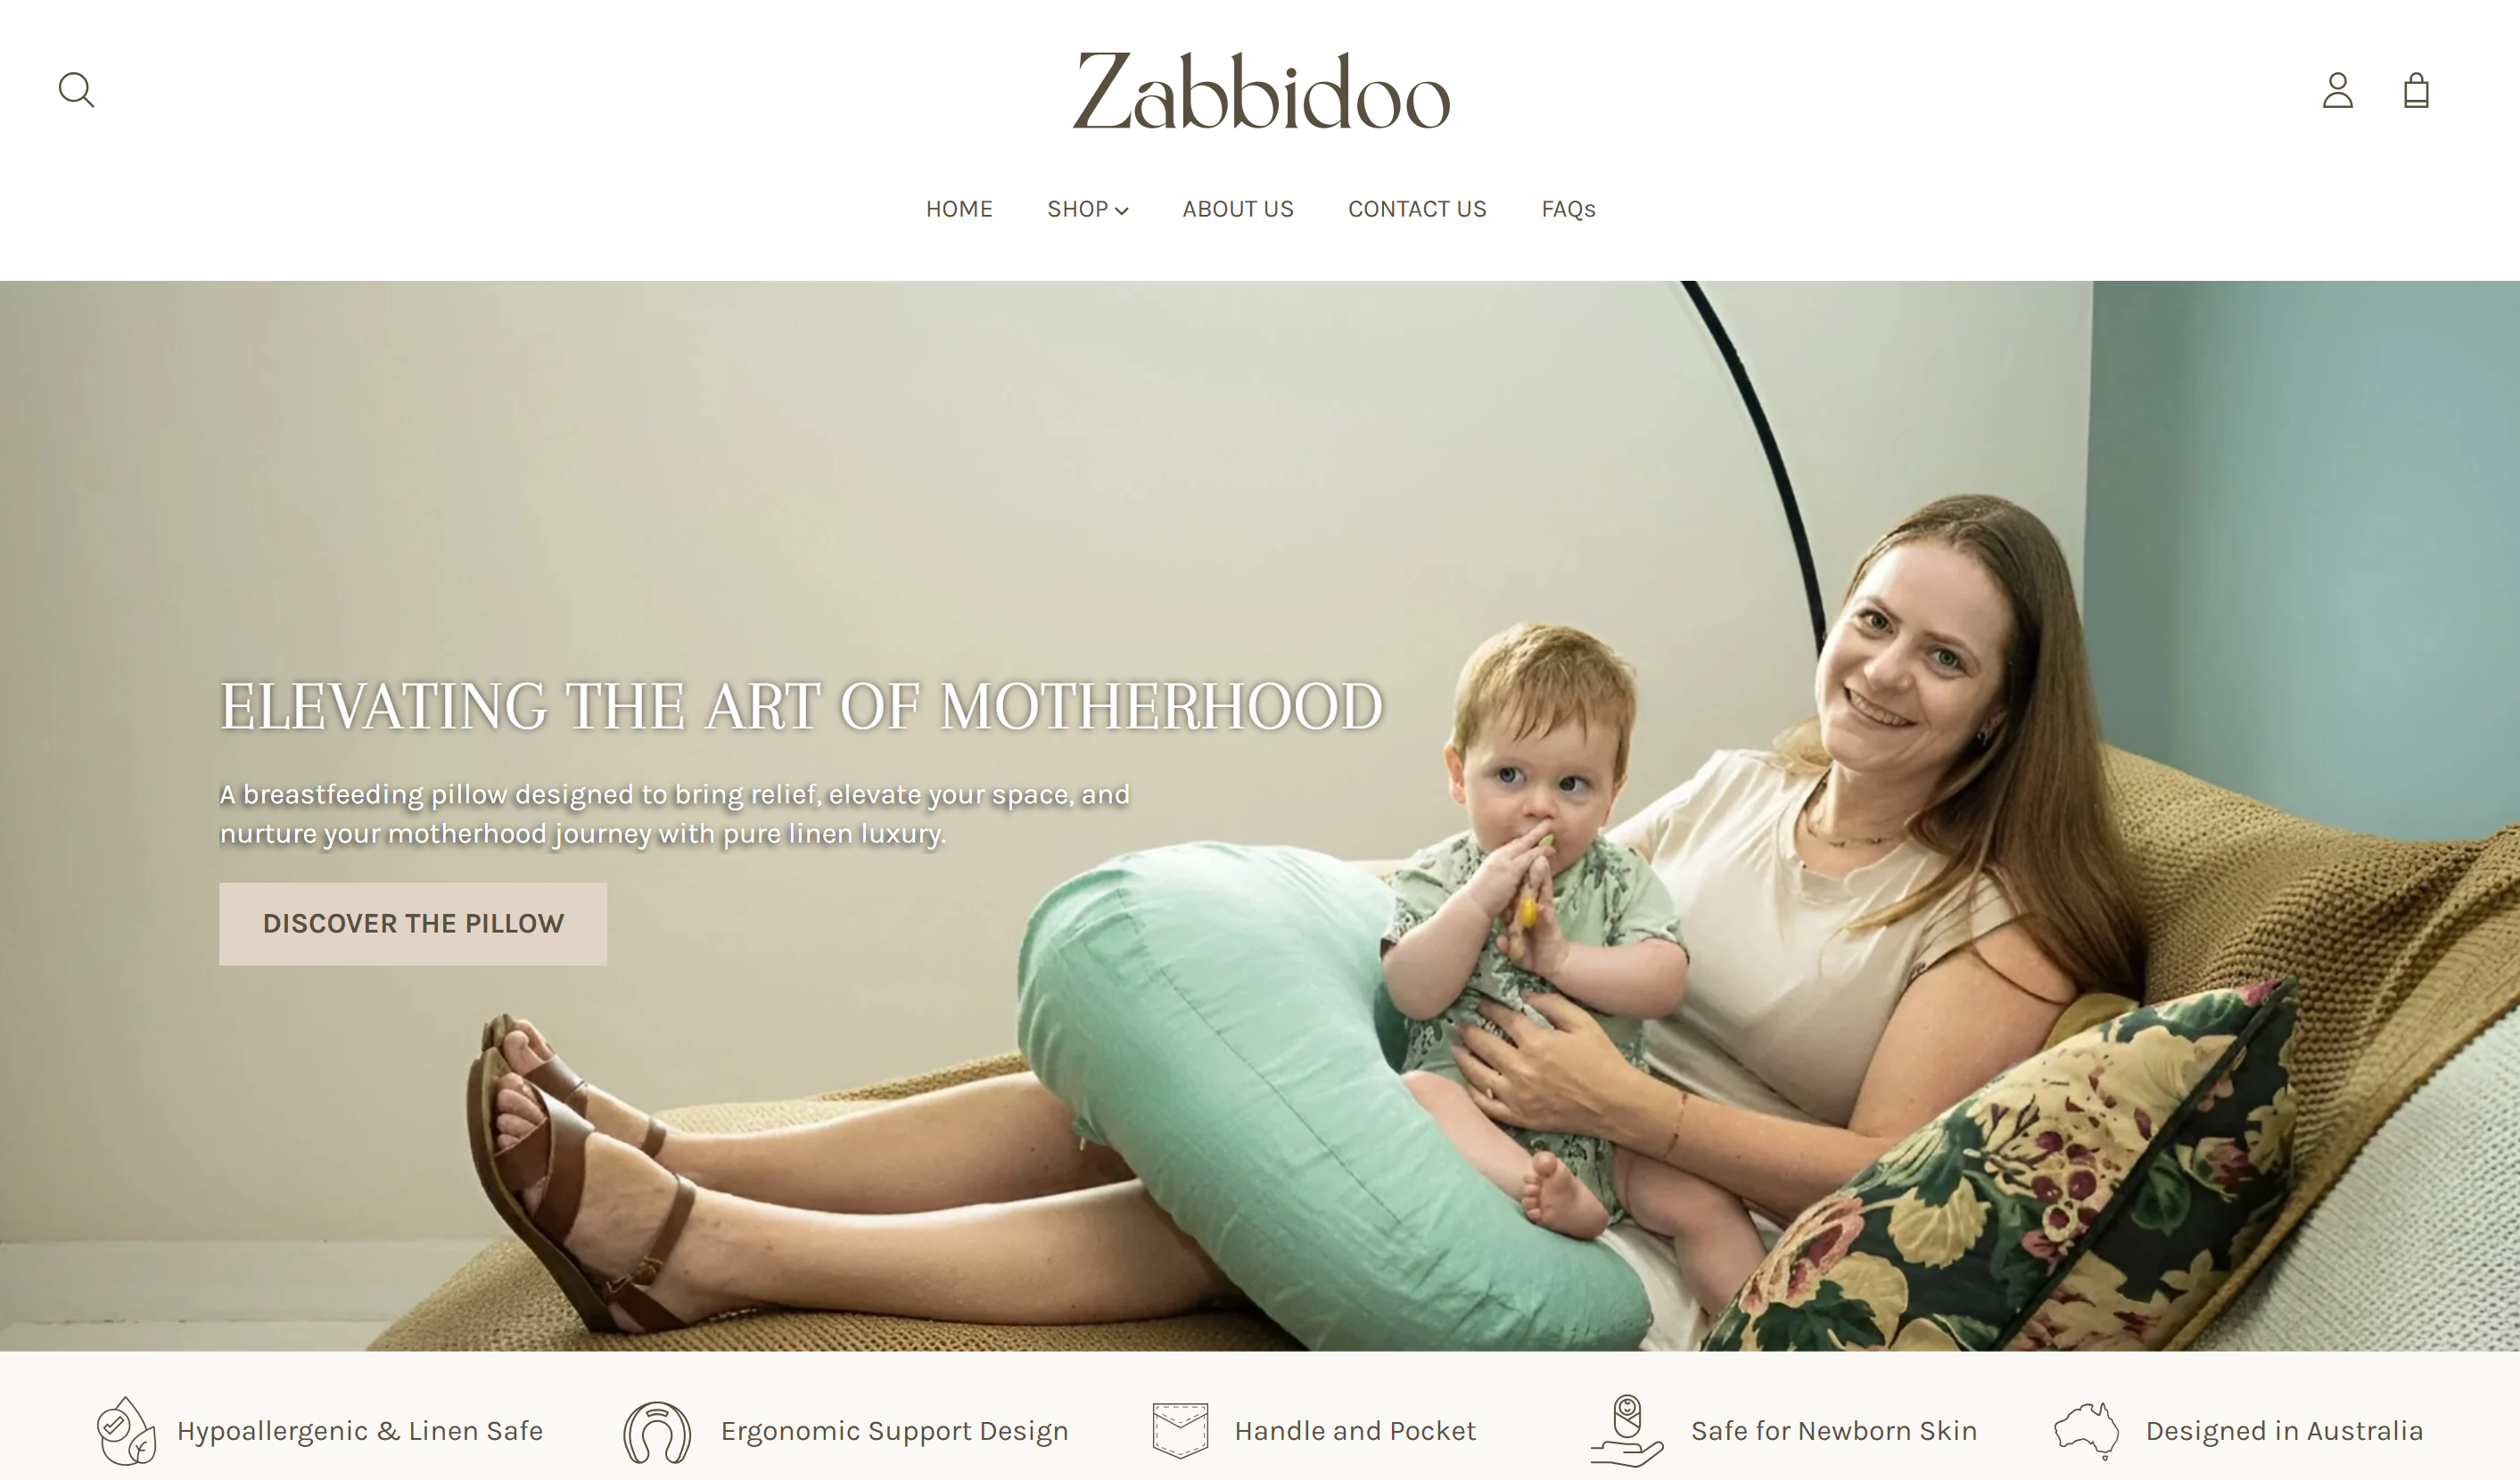
We designed it as a practical support for posture and positioning, not a substitute for a lactation consultant’s assessment of latch or oral anatomy. Used alongside professional guidance, it’s one less thing working against your comfort during a feed. Have a look at the nursing pillow on our site to see if it fits what your feeds need right now.
FAQ
How to make a baby latch less painful?
Bring your baby to breast height rather than leaning down to them, with their nose level with your nipple before they open wide. If pain continues past the first minute of a feed, break the latch gently and try again with a deeper, wider mouthful.
Why does breastfeeding hurt even with a good latch?
Pain despite a seemingly good latch can point to thrush, dermatitis, early ductal inflammation or a tongue tie that isn’t obvious on casual inspection. Persistent nipple pain is often multifactorial, so a lactation consultant or GP assessment helps rule these in or out.
How to relieve pain in breasts while weaning?
Gentle, gradual reduction in feeds or pumping sessions, along with cool compresses and supportive bras, generally eases discomfort during weaning. Avoid vigorous massage or aggressive pumping to “empty” the breast, since this can worsen swelling and pain rather than relieve it.
Is it supposed to hurt when my baby latches?
Brief tenderness in the first moments of a feed during the early weeks can be normal, but sharp, stabbing or ongoing pain is not something to push through. Pain that persists or worsens usually means the latch needs adjusting or a professional needs to check for an underlying cause.
Sources
- Academy of Breastfeeding Medicine protocol 36: The mastitis spectrum (2022)
- Why are my nipples sore? | Australian Breastfeeding Association
- Mastitis | healthdirect
- Identifying the cause of breast and nipple pain during lactation | BMJ